



Not medical advice — written by Ngoc Vietsmall, who is not a healthcare professional.
This article summarises publicly available medical information for general readers. It cannot account for your history, medication or symptoms, and it is not a diagnosis or a treatment plan. Any dose mentioned comes from published labelling or guidelines — only your own prescriber can decide what is right for you.
Always speak to a doctor or pharmacist before starting, stopping or changing any treatment. If symptoms are severe or getting worse, seek urgent care. Full disclaimer · How this is written
If youve ever heard a rhythmic whoosh in just one ear, youve experienced unilateral pulsatile tinnitus. Its not a disease itselfjust a signal that something in or around your ear is moving with your heartbeat. The cause can be harmless (like a fleeting bloodpressure rise) or the warning bell of a serious vascular issue that needs prompt attention.
Below youll find a friendly, stepbystep guide that cuts through the medical jargon, highlights the most common culprits, shows you what to look for in a physical exam, and explains which imaging tests really matter. By the end, youll know when to breathe easy and when to call your doctor right away.
Quick Overview
Most Common Causes
Prevalence vs. Urgency
| Cause | How Often | Urgency |
|---|---|---|
| Idiopathic intracranial hypertension / venous sinus stenosis | 30% | Moderate treatable, monitor |
| Arteriovenous fistula (dural AVF) | 5% | High may need endovascular repair |
| Atherosclerotic carotid or vertebral stenosis | 15% | Lowtomoderate manage risk factors |
| Paraganglioma or glomus tumor | 2% | Moderate surgical evaluation |
| Middleear ossicular fixation (otosclerosis) | 10% | Low hearingaid or surgery |
When Is It Dangerous?
RedFlag Checklist
- Sudden onset of a loud, rhythmic sound
- Neurologic symptoms (weakness, vision changes, facial numbness)
- Bruit audible to the examiner
- Worsening with Valsalva or head movement
- Associated hearing loss or balance disturbance
If any of these appear, seek medical attention promptlytime can make a big difference.
Vascular Causes
What Is the Most Common Vascular Cause?
Idiopathic Intracranial Hypertension (IIH)
IIH, often linked with venous sinus stenosis, tops the list. The elevated intracranial pressure pushes on the venous sinuses, creating that characteristic pulsesynchronized hum. Many patients are young, overweight women, but the condition can affect anyone.
Arteriovenous Fistula (Dural AVF)
Key Imaging Signs
A dural AVF creates an abnormal direct connection between arteries and veins in the dura. On MRI the hallmark is arterialized venous flowveins look brighter than they should on timeofflight MRangiography. A study shows that early detection dramatically improves outcomes.
Case Snippet
Consider Maya, a 42yearold who described a whooshing that gets louder when she tilts her head back. After a bedside auscultation captured a bruit, a contrastenhanced MRvenogram revealed a transversesigmoid sinus AVF. She underwent successful endovascular embolization and the tinnitus faded within weeks.
Atherosclerotic Stenosis
Typical Locations
Plaque buildup at the carotid bulb or vertebral artery can generate turbulent flow audible in the ear. This is often the answer when a patient mentions a persistent heartbeat that does not change with position.
Basilar Artery Loop
When to Suspect
If imaging shows an anomalous basilar artery hugging the inner ear and the tinnitus persists despite normal sinus flow, think vascular loop syndrome. Surgical decompression is an option, but most patients improve with conservative measures.
Paraganglioma / Glomus Tumor
Clinical Clues
These highly vascular tumors sit at the jugular bulb or middle ear. You might notice a reddish mass behind the tympanic membrane or a persistent bruit that doesnt change with Valsalva. Surgical removal often resolves the sound.
NonVascular Causes
MiddleEar & InnerEar Pathology
Otosclerosis & Ossicular Fixation
Stiffening of the tiny bones in the middle ear can create a conductive hearing loss and a subtle pulsatile noise. A simple tympanogram can spot the problem, and stapedectomy surgery often restores normal hearing.
Intracranial Hypertension Without Stenosis
Intermittent Pulsatile Tinnitus
Even without a measurable venous narrowing, raised CSF pressure can amplify vascular sounds. Lumbar puncture opening pressure and opticnerve sheath imaging help confirm the diagnosis.
CSF Leak & SkullBase Defects
Positional Changes
When a tiny tear lets CSF escape, the pressure dynamics shift with head positiontinnitus may come and go, and you might also notice a salty taste or clear drainage from the nose.
Systemic Factors
BloodPressure, Anemia, Thyroid
High blood pressure, low hemoglobin, or hyperthyroidism can all make your blood flow louder. Treating the underlying condition often quiets the ear.
Clinical Evaluation
Core History Questions
Key Points to Ask
- When did the sound start? Sudden versus gradual?
- Is it constant, intermittent, or does it come and go?
- Does it change with head position, exercise, or Valsalva?
- Any associated hearing loss, dizziness, or visual symptoms?
- Do you have high blood pressure, recent weight change, or thyroid issues?
Physical Exam Pearls
Auscultation & More
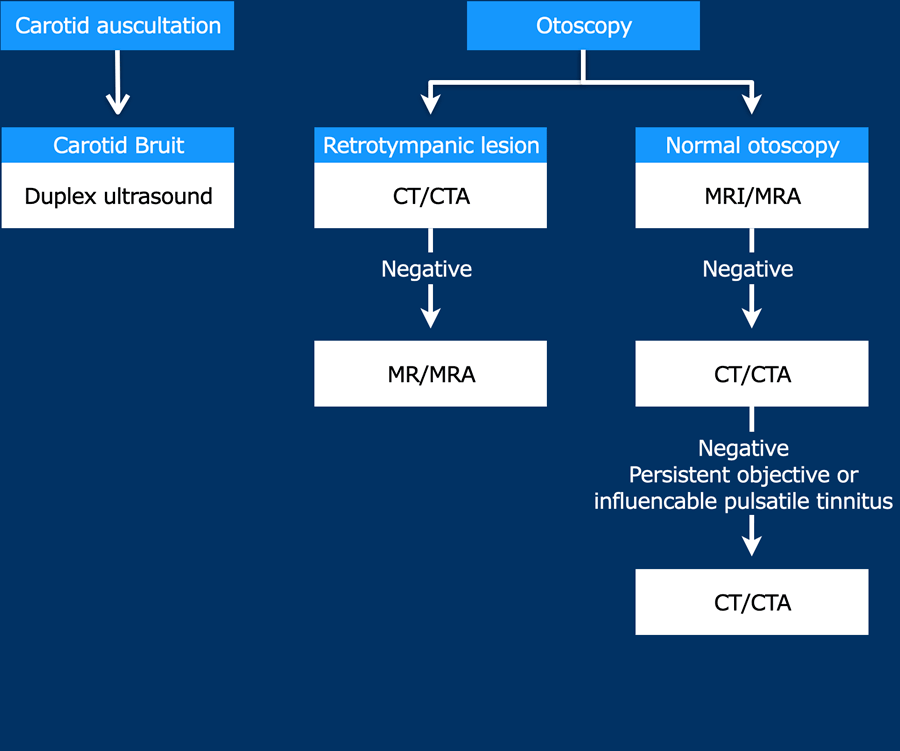
Place a stethoscope over the mastoid, the neck, and even the orbit. A detectable bruit often points to a vascular source. Palpate for thrills, and run a quick cranialnerve screenespecially CN VI (abducens) for increased intracranial pressure.
When to Image Urgently
RedFlag Triggers
If you spot any of the redflag items above, order imaging without delay. Early diagnosis can prevent irreversible neurologic damage.
Imaging WorkUp & MRI Protocol
Recommended MRI Sequence
Pulsatile Tinnitus MRI Protocol
A dedicated protocol includes:
- T1weighted 3D spoiled gradient echo (pre and postcontrast)
- T2weighted highresolution (to see innerear fluids)
- Timeofflight MRangiography (for arterial flow)
- Contrastenhanced MRvenography (to map venous sinuses)
This combo captures both arterial and venous lesions in one session.
CT Angiography or DSA?
When to Add
If MRI suggests a dural AVF or a bony abnormality, a CT angiogram (CTA) or digital subtraction angiography (DSA) offers finer detail and can guide endovascular treatment.
Interpreting Common Findings
Quick Reference Table
| Imaging Sign | Likely Diagnosis |
|---|---|
| Enlarged transverse sinus with flow void | Venous sinus stenosis / IIH |
| Arterialized venous channels on MRV | Dural AVF |
| Calcified mass at jugular bulb | Paraganglioma |
| Stiff ossicles on CT | Otosclerosis |
Management & Treatment Options
Treat the Underlying Cause
Vascular Interventions
For a stenotic sinus, stenting can relieve pressure and silence the noise. Dural AVFs often respond to coil embolization. Both procedures have high success rates and short recovery times.
NonVascular Therapies
When the culprit is otosclerosis, a stapedectomy offers great relief. For CSF leaks, surgical repair of the skullbase defect is curative.
Medical Therapies
Weight Loss & Acetazolamide
Patients with IIH benefit from weight reduction and carbonic anhydrase inhibitors like acetazolamide, which lower intracranial pressure.
Lifestyle Tweaks
Simple Changes That Help
- Limit caffeine and alcohol, both of which can amplify vascular tone.
- Maintain a balanced sodium intakeexcess salt can raise intracranial pressure.
- Practice gentle neck stretches; some people find that avoiding extreme head positions reduces the sound.
Is Pulsatile Tinnitus Dangerous?
HighRisk Entities
Yes, when the sound stems from a dural AVF, rapidly expanding tumor, or severe intracranial hypertension, time is of the essence. Early referral to a neurootologist or interventional radiologist can be lifesaving.
Frequently Asked Questions (SnippetReady)
What is the most common cause of pulsatile tinnitus?
Answer
The leading cause is idiopathic intracranial hypertension/venous sinus stenosis, accounting for about onethird of cases.
Can pulsatile tinnitus change with head position?
Answer
Yespositional changes often point to venous sinus abnormalities or CSFpressurerelated mechanisms.
Is unilateral pulsatile tinnitus dangerous?
Answer
It can be, especially if caused by a dural arteriovenous fistula or an expanding tumor; redflag signs demand immediate imaging.
What MRI protocol should I request?
Answer
A dedicated protocol with timeofflight MRangiography plus contrastenhanced MRvenography, plus highresolution T2 sequences, is considered standard.
How is intermittent pulsatile tinnitus evaluated?
Answer
Intermittency suggests a dynamic vascular source; repeat imaging or Doppler ultrasound during symptomatic episodes can be helpful.
Bottom Line & Next Steps
Unilateral pulsatile tinnitus is a symptom with a broad differentialfrom benign bloodflow quirks to serious vascular lesions. A focused history, a quick bedside exam, and a targeted MRI protocol can separate the common from the critical in a matter of days.
If youre hearing a rhythmic whoosh in one ear, start by noting when it occurs and whether it changes with movement. Share those details with your ENT or neurologist, and ask for the pulsatile tinnitus MRI protocol if imaging is recommended. Early detection often means simple, effective treatmentand a quieter life.
Have you or someone you know dealt with pulsatile tinnitus? What turned out to be the cause, and how did the journey unfold? Feel free to reach out with your story or any lingering questionswere all ears.








