



Not medical advice — written by Ngoc Vietsmall, who is not a healthcare professional.
This article summarises publicly available medical information for general readers. It cannot account for your history, medication or symptoms, and it is not a diagnosis or a treatment plan. Any dose mentioned comes from published labelling or guidelines — only your own prescriber can decide what is right for you.
Always speak to a doctor or pharmacist before starting, stopping or changing any treatment. If symptoms are severe or getting worse, seek urgent care. Full disclaimer · How this is written
If one leg suddenly looks puffier than the other and leaves a little dent when you press it, youre probably dealing with unilateral pitting edema. The good news? Most of the time the cause is treatable, and a focused history plus a quick bedside exam can point you in the right direction. Below youll find a concise, stepbystep rundown of the most common causes, how to tell them apart, and what to do next no medical jargon, just the facts you need to act confidently.
What Is Pitting?
Definition and Recognition
Pitting describes the tiny indentation that stays for a few seconds after you press on swollen skin with a fingertip. If the swelling disappears right away, its likely nonpitting edema, which has a different set of culprits.
Quick bedside test
1. Use the pad of your index finger.
2. Press firmly on the swollen area for about five seconds.
3. Release and watch the skin. A visible pit that slowly fills in is classic pitting edema.
Pitting vs NonPitting
Understanding whether the edema is pitting or not is like sorting socks before doing laundry it tells you which basket (or specialty) to put the problem in. Pitting is most often linked to vascular or fluid overload issues, while nonpitting points toward lymphatic blockage or certain systemic diseases.
Top Causes Overview
Venous Causes
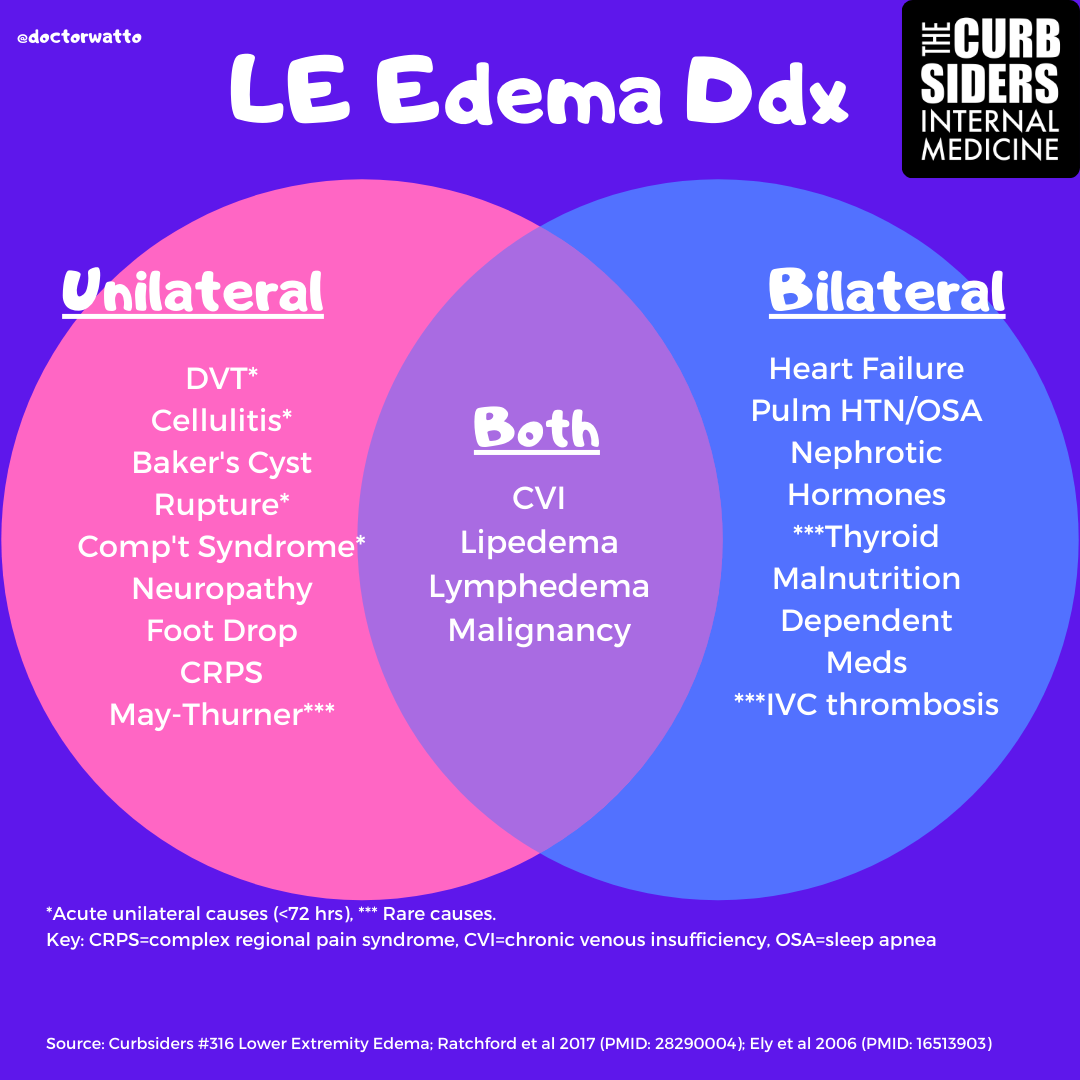
Chronic Venous Insufficiency
Think of your veins as highways that should let blood flow back to the heart. When the highways get clogged or their walls weaken, fluid drips out into the surrounding tissue, creating that telltale dent. Its the single biggest culprit for unilateral pitting edema in people over 50.study
Deep Vein Thrombosis (DVT)
A clot that forms in a deep leg vein can block blood flow, leading to rapid swelling that is almost always pitting. DVT is a redflag emergency if you notice sudden tightness, warmth, or pain, get an ultrasound right away.
Lymphatic Causes
Primary & Secondary Lymphedema
Lymphatic vessels are the bodys drainage pipes. When theyre damaged (postsurgery, radiation) or congenitally underdeveloped, fluid builds up. Unlike venous swelling, lymphedema is usually nonpitting and may feel rubbery. The Stemmer sign (inability to pinch a fold of skin at the base of the toe) helps differentiate the two.
Systemic Causes
Cardiac, Renal, Hepatic
Heart failure, nephrotic syndrome, and cirrhosis typically cause bilateral leg swelling, but early disease can start on one side. Look for accompanying clues: shortness of breath with heart trouble, frothy urine with kidney issues, or a swollen belly with liver disease.
Infection & Trauma
Cellulitis, Hematoma
Skin infection (cellulitis) can make the leg red, hot, and painful, often with pitting edema. A bruise or hematoma from an injury also produces a localized swelling that may pit when you press.
Rare But Important
Pelvic Tumors, Constrictive Pericarditis
Large pelvic masses can compress veins, leading to unilateral swelling. Constrictive pericarditis a thickened heart sac can back up blood flow and manifest as leg edema before other heart symptoms appear.
Diagnostic StepbyStep
History Checklist
Start with a friendly conversation, not an interrogation. Ask yourself (or the patient) the following:
Sample questionnaire
- When did the swelling first appear?
- Is it worse after standing, walking, or at night?
- Any pain, redness, or warmth?
- Recent travel, long flights, or immobilization?
- History of surgery, cancer, or radiation?
- Current medications (especially steroids or NSAIDs)?
- Any changes in weight, urine output, or breathing?
Physical Exam
Inspect, palpate, and compare both limbs. Use the 04 pitting grading scale (0=no pit, 4=deep pit lasting >10seconds). Check skin temperature, pulses, and nerve function. A quick table can help you keep the details straight.
Pitting grading table
| Grade | Description |
|---|---|
| 0 | No visible pit |
| 1+ | Very shallow pit, fills instantly |
| 2+ | Deeper pit, fills in 12seconds |
| 3+ | Noticeable pit, fills in 35seconds |
| 4+ | Deep pit, persists >10seconds |
Labs & Imaging
Imaging choices
Duplex ultrasound is the first line for DVT and venous reflux. If you suspect lymphatic involvement, a lymphoscintigraphy can map the drainage pathways. For systemic causes, a basic metabolic panel, liver function tests, and a BNP (braintype natriuretic peptide) level give clues about heart or kidney disease. When a pelvic mass is on the radar, a CT or MRI of the abdomen/pelvis is warranted.
Management Strategies
Acute vs Chronic
Not all swelling needs the same roadmap. Acute causes like DVT or cellulitis demand urgent treatmentanticoagulation or antibioticswhile chronic venous insufficiency lives with longterm measures.
Treatment pearls
- DVT: Immediate anticoagulation, compression stockings after the first week, and followup Doppler.
- Cellulitis: Oral antibiotics (often a cephalexin or clindamycin), limb elevation, and monitoring for spread.
- Venous insufficiency: Graduated compression (2030mmHg), calfmuscle exercises, and occasional venous ablation procedures.
- Lymphedema: Manual lymphatic drainage, compression garments, and meticulous skin care to prevent infection.
Lifestyle Tips
Selfcare ideas
Small daily habits can make a world of difference. Elevate the affected leg above heart level for 15minutes three times a day. Keep skin moisturized to avoid cracks that invite infection. If youre overweight, gentle weight loss reduces pressure on veins. A lowsalt diet helps the kidneys excrete excess fluid. And yesthose compression stockings might feel snug, but theyre your best buddy for keeping the fluid from pooling.
FollowUp Plan
Schedule a review within a week for any acute condition. For chronic issues, aim for a quarterly checkin, especially if youve started new compression therapy or medications. Keep an eye on redflag signssudden pain, swelling of the other leg, shortness of breathand act fast.
When To Call 911
RedFlag Checklist
Immediate actions
- Sudden, severe calf pain with swelling (possible DVT).
- Rapidly expanding, hot, red leg (cellulitis spreading).
- Swelling accompanied by chest pain, shortness of breath, or palpitations (possible heart failure or pulmonary embolism).
- Sudden weakness or numbness in the foot (vascular compromise).
If any of these pop up, dont waitcall emergency services right away.
RealWorld Cases
Case One: Venous
Lessons learned
Maria, 68, noticed her left ankle swelling after gardening for an hour. The edema was pitting, warm, and slightly discolored. An ultrasound confirmed chronic venous insufficiency with mild reflux. She started wearing 30mmHg compression stockings, did ankle pumps each morning, and lost 5kg over three months. Within six weeks her leg looked noticeably better and the dent faded.
Case Two: DVT
Key takeaways
James, 29, returned from a crosscountry bike ride with a painful, swollen right calf. He thought it was just muscle soreness. A quick press left a deep pit, and an urgent Doppler revealed a proximal DVT. He began anticoagulation, wore compression, and completed a threemonth course without complications. The story underscores why any sudden unilateral pitting swelling after prolonged immobility deserves a clot check.
Conclusion
Unilateral pitting edema can be unsettling, but with the right questions, a simple bedside test, and a clear diagnostic roadmap, you can separate a harmless venous blush from a lifethreatening clot. Remember: look for the pitting sign, chart the history, check for red flags, and dont hesitate to call for help when the situation feels urgent. If you notice swelling that wont quit, reach out to a healthcare professional early action saves time, stress, and sometimes even lives. Stay curious, stay proactive, and keep those legs happy!








