Not medical advice — written by Ngoc Vietsmall, who is not a healthcare professional.
This article summarises publicly available medical information for general readers. It cannot account for your history, medication or symptoms, and it is not a diagnosis or a treatment plan. Any dose mentioned comes from published labelling or guidelines — only your own prescriber can decide what is right for you.
Always speak to a doctor or pharmacist before starting, stopping or changing any treatment. If symptoms are severe or getting worse, seek urgent care. Full disclaimer · How this is written
If you've been keeping an eye on heart failure news (or you've just heard a friend mention a new drug for heart failure), you're probably wondering what's actually new this year and why it matters to you or a loved one. This overview summarizes information from FDA labels and clinical guidelines; it is not medical advice. Only your healthcare provider can determine what is right for you. The short answer? 2024 brought three FDA-approved drugs that shift the treatment approach, and the latest guideline updates have formally incorporated them. Let's dive straight into the facts.
Quick Answer Overview
Answer #1: The three agents now on the market are SGLT2 inhibitors (dapagliflozin, empagliflozin), Sotatercept (Winrevair), and Resmetirom (Rezdiffra). All three are now part of the updated recommendations across the full spectrum of left-ventricular ejection fraction (LVEF), from classic HFrEF to the newly-covered HFpEF.
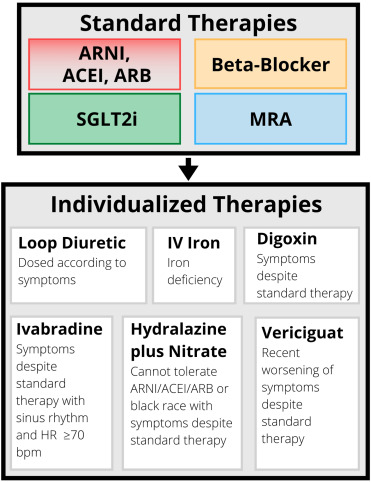
Answer #2: While these drugs are associated with improved survival and quality of life, they also bring new considerations—kidney function, injection-site reactions, cost, and possible drug-drug interactions. Integrating them safely with the traditional quadruple therapy (ARNI+beta-blocker+MRA+SGLT2i) is a key focus of current heart-failure care.
Guideline Landscape 2024
The 2024 updates from the American College of Cardiology (ACC), American Heart Association (AHA), and the European Society of Cardiology (ESC) have finally caught up with the data. If you want to see the exact tables, grab the ACC heart failure guidelines 2024 PDF and the ESC heart failure guidelines 2024 PDF. Both documents are free after a quick registration.
What changed? In 2023, SGLT2 inhibitors were considered for HFrEF only. In 2024, they are a class-I recommendation for *all* ejection-fraction categories, and Sotatercept earned a strong recommendation for HFpEF with LVEF≥50%. Meanwhile, the older drugs—ARNI, beta-blockers, and mineralocorticoid receptor antagonists (MRA)—remain foundational, forming the backbone of the updated algorithm.
2024 vs. 2023 Guideline Snapshot
| Feature | 2023 Guideline | 2024 Guideline |
|---|---|---|
| SGLT2i Role | Consider for HFrEF only | Class-I for all EF ranges |
| Sotatercept | Investigational | Recommend for HFpEF≥50% |
| Resmetirom | Not yet FDA-approved | Approved for metabolic HF (selected pts) |
New Drugs for Heart Failure 2024
1. SGLT2 Inhibitors – First-Line for Everyone
These were not originally diabetes pills; they turned out to be beneficial for heart failure. By nudging the kidneys to excrete more sodium and glucose, they reduce volume overload and improve myocardial metabolism.
Key trials: The 2024 extensions of EMPEROR-PreservePLUS and DAPA-HFALL showed reductions in mortality across HFrEF, HFmrEF, and HFpEF. The data are now baked into the 2024 heart failure guidelines, which list SGLT2 inhibitors as a recommended component of initial therapy.
Label information:
- The FDA label states starting doses (dapagliflozin 5 mg daily or empagliflozin 10 mg) with a maximum of 10 mg daily for both; however, the actual dose and any titration are determined by your prescriber.
- Renal function is monitored: the label notes use can continue down to an eGFR of 30 mL/min/1.73m², with discontinuation recommended below 20.
- Reported side effects include genital yeast infections and mild dehydration, especially in the first few weeks.
SGLT2i Dosing Information from the Label
| Drug | Label-Stated Starting Dose | Label-Stated Maximum Dose | Renal Consideration per Label | Common Side Effects |
|---|---|---|---|---|
| Dapagliflozin (Farxiga) | 5 mg daily | 10 mg daily | eGFR ≥30 mL/min/1.73m² | Genital infection, volume depletion |
| Empagliflozin (Jardiance) | 10 mg daily | 10 mg daily | eGFR ≥30 mL/min/1.73m² | Similar to dapagliflozin |
Your prescriber will decide the appropriate dose for you based on your individual health status.
2. Sotatercept – The First HFpEF-Specific Agent
Imagine a drug that literally traps a protein that was sabotaging your heart's structure—that's Sotatercept in a nutshell. It binds activin-type II receptors, modulating the growth-factor pathway that drives fibrosis.
The OSIRIS-HF Phase 3 trial (2024) enrolled over 2,000 patients with LVEF ≥50% and showed a reduction in heart-failure hospitalizations over 18 months. The drug is administered as a subcutaneous injection every four weeks.
Safety snapshot: Injection-site redness or mild hypertension have been reported in a portion of patients. Labs should include hemoglobin (it can rise modestly) and routine electrolytes.
3. Resmetirom – A Metabolic Twist for Heart Failure
Resmetirom is not a heart-specific drug; it is a thyroid-hormone mimetic that clears liver fat, indirectly easing the heart's workload. The CardioMetabolic Health 2024 review highlighted an improvement in LVEF among participants with nonalcoholic fatty liver disease (NAFLD)-related HF. It is taken as a once-daily oral tablet. The main caveat? Thyroid function tests are typically monitored every three months; overactivation can cause palpitations.
Integrating Into Therapy
General Approach Outlined by Guidelines
Guidelines describe the following general considerations, which a clinician individualizes for each patient:
- Diagnosis and LVEF are confirmed by the clinician using echo, labs, and symptom assessment.
- A foundation of ARNIs (or ACEi/ARB if needed), beta-blockers, and MRAs is established, with each agent adjusted to target doses as tolerated.
- An SGLT2 inhibitor is recommended for all ejection-fraction ranges.
- For HFpEF ≥50% with persistent symptoms after step 3, Sotatercept may be considered.
- Resmetirom may be used in patients who have significant hepatic steatosis or metabolic syndrome and who tolerate the preceding steps.
Clinical Features and Associated Drug Considerations
| Clinical Feature | Sotatercept | Resmetirom |
|---|---|---|
| LVEF ≥50% | May be considered | Not specifically indicated |
| Significant NAFLD | Not specifically indicated | May be considered |
| Prior SGLT2i intolerance | May be an alternative pathway | May be an alternative pathway |
Benefits vs. Risks – A Balanced View
It is tempting to label any new drug as a miracle, but real life is messier. Here is a quick, no-spin rundown.
Benefits
- Survival: Evidence suggests improved survival in high-risk groups.
- Fewer hospital trips: Landmark trials showed reduced hospitalization rates.
- Quality-of-life uplift: Patients reported better NYHA functional class and less fatigue.
Risks & Caveats
- Kidney safety: Renal monitoring is recommended for SGLT2 inhibitors; dose adjustments may be needed.
- Injection concerns: Sotatercept's monthly injection can cause bruising; rotating injection sites is a common strategy.
- Cost: These are premium drugs; insurance preauthorization is often required.
- Drug interactions: Potassium-sparing agents require attention when combined with MRAs and certain SGLT2 inhibitors.
When you meet with your cardiologist, it can be helpful to ask about your lab results, any dizziness, and out-of-pocket costs. This conversation makes the risk-benefit balance tangible.
Helpful Resources
To stay ahead, consider bookmarking the following trusted sources:
- PubMed 2024 heart-failure update (PMID38806171) – the primary source for guideline changes.
- American Heart Association Top HF News of 2024 – a concise news roundup.
- FDA's Mid-Year Review of New Cardiovascular Drugs 2024 – official approval letters for Sotatercept and Resmetirom.
All of these are public, peer-reviewed, and free to access. When you read the original studies, you will see the same numbers summarized here, which builds confidence in the recommendations.
Conclusion
2024 truly reshaped how heart failure is approached. SGLT2 inhibitors have moved from nice-to-have to recommended for every patient, Sotatercept finally gives HFpEF a dedicated therapy, and Resmetirom adds a metabolic twist for those with liver-fat-driven disease. The new 2024 heart failure guidelines stitch these advances together, urging clinicians to personalize care while staying vigilant about safety and cost.
Take what you have learned, discuss it with your healthcare team, and do not shy away from asking questions—your heart deserves that level of attention. If you have tried any of these drugs or have concerns about them, sharing experiences can help everyone navigate this evolving landscape with confidence.