



Not medical advice — written by Ngoc Vietsmall, who is not a healthcare professional.
This article summarises publicly available medical information for general readers. It cannot account for your history, medication or symptoms, and it is not a diagnosis or a treatment plan. Any dose mentioned comes from published labelling or guidelines — only your own prescriber can decide what is right for you.
Always speak to a doctor or pharmacist before starting, stopping or changing any treatment. If symptoms are severe or getting worse, seek urgent care. Full disclaimer · How this is written
If youve ever wondered why doctors keep mentioning thiazides when talking about blood pressure or swelling, youre not alone. In a nutshell, thiazide diuretics are a family of kidneyacting medicines that help your body get rid of excess salt and water, which can lower blood pressure and reduce edema. Understanding how this family is split pure thiazides versus thiazidelike agents along with their common names, labeled dosing information, and sideeffect profile, can be helpful whether youre a patient, a caregiver, or a healthcare student.
Below, well walk through general information about thiazide diuretics classification, from the chemistry that defines the group to safety considerations. This overview aims to provide clear and enjoyable information for educational purposes.
What Defines Thiazides
At its core, a thiazide diuretic is a drug that blocks the sodiumchloride transporter in the distal convoluted tubule of the kidney. This little transporter normally pulls sodium and chloride back into the bloodstream; when its blocked, more of those ions and the water that follows are flushed out in the urine. The classic chemical signature is the benzothiadiazine ring, which gives the original thiazides their name.
Pure Thiazide vs. ThiazideLike
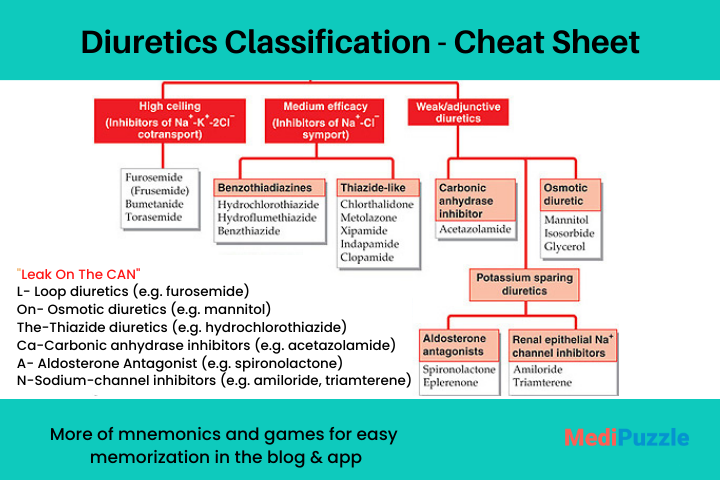
While the term thiazide is often used loosely, theres a subtle but important split. Pure thiazides (like hydrochlorothiazide and chlorothiazide) contain the exact benzothiadiazine core. Thiazidelike diuretics (such as chlorthalidone and indapamide) mimic the mechanism but have slightly different structures, which can affect potency, duration, and sideeffect risk.
| Agent Type | Examples | Key Structural Feature | Typical HalfLife |
|---|---|---|---|
| Pure Thiazide | Hydrochlorothiazide, Chlorothiazide | Benzothiadiazine ring | 615hours |
| Thiazidelike | Chlorthalidone, Indapamide, Metolazone | Modified sulfonamidebased core | 4060hours (chlorthalidone) |
Mechanism of Action
The thiazide diuretics mechanism of action centers on the Na/Cl symporter in the distal convoluted tubule. By inhibiting this transporter, the drugs reduce sodium reabsorption, which drags water along with it. The resulting natriuresis (loss of sodium) and diuresis (increased urine output) lower extracellular fluid volume, easing the workload on the heart and blood vessels.
Why It Matters for Hypertension vs. Edema
When a person has high blood pressure, even a modest drop in fluid volume can translate into a noticeable dip in arterial pressure. For edemathink swelling associated with conditions like heart failure or liver diseasethe extra fluid removal may provide symptom relief. Thats why thiazides are often considered a firstline option for many hypertension cases and a reliable adjunct for edema management, as determined by a healthcare provider.
Drug Classification
Pure Thiazide Diuretics
- Hydrochlorothiazide (HCTZ)
- Chlorothiazide
- Bendroflumethiazide
ThiazideLike Diuretics
- Chlorthalidone
- Indapamide
- Metolazone (borderline)
Comparison Table
| Drug Name | Brand Names | Labeled Dose Range | Onset / Duration | Key Uses | Major Side Effects |
|---|---|---|---|---|---|
| Hydrochlorothiazide | Microzide, Esidrix | 12.5–50 mg daily (per label) | 24h / 615h | Hypertension, mild edema | Hypokalemia, hyperuricemia |
| Chlorthalidone | Hygroton, Thalitone | 12.5–25 mg daily (per label) | 26h / 4060h | Hypertension, resistant HTN | Electrolyte shifts, gout flare |
| Indapamide | Lozol, Natacyn | 1.25–2.5 mg daily (per label) | 23h / 1218h | Hypertension, heart failure | Hypokalemia, dizziness |
Clinical Uses & Dosing
Thiazide diuretics are remarkably versatile. Below is a quick snapshot of the most common indications and how dosing is typically described in prescribing information.
Hypertension
Clinical guidelines often list thiazides as a firstline option, either alone or combined with an ACE inhibitor, ARB, or calciumchannel blocker. Prescribing information indicates that low doses are often used to help achieve blood pressure goals. Only a prescriber can determine the appropriate dose for an individual patient.
Edema
For fluid overload due to heart failure, cirrhosis, or nephrotic syndrome, thiazides (or thiazidelike agents) may add an extra diuretic push when loop diuretics alone arent enough. Doses vary based on individual needs and kidney function, as determined by a clinician.
Niche Uses
- Preventing calciumcontaining kidney stones (by reducing urinary calcium excretion).
- Adjunct in osteoporosis treatmentsome evidence suggests some thiazidelike agents may modestly increase bone mineral density.
Standard Dose Ranges
The following ranges reflect typical labeling information. A prescriber determines the specific dose and frequency for each patient.
- Hydrochlorothiazide: Labels indicate ranges such as 12.5–50 mg once daily.
- Chlorthalidone: Labels indicate ranges such as 12.5–25 mg once daily.
- Indapamide: Labels indicate ranges such as 1.25–2.5 mg daily (often XR formulation).
- Metolazone: Labels indicate ranges such as 2.5–10 mg daily, often used in renal impairment.
Adjustments for Special Populations
Elderly patients and those with reduced renal function often require careful monitoring and potentially lower starting doses. For example, a clinician might start with a lower dose and check electrolytes regularly. Only a healthcare provider can make these adjustments.
Side Effects & Safety Profile
Like any medicine, thiazides arent without tradeoffs. The most common adverse events stem from the very electrolyte shifts that give them their therapeutic punch.
Common Side Effects
- Low potassium (hypokalemia) can cause muscle cramps, fatigue.
- Low sodium (hyponatremia) may lead to headache or confusion.
- Elevated uric acid (hyperuricemia) risk of gout flare.
- Higher blood sugar (hyperglycemia) a concern for diabetics.
Rare but Serious Risks
Severe allergic reactions, pancreatitis, and profound electrolyte imbalance are rare but documented. Routine monitoringespecially in the first weekshelps catch problems early.
Monitoring Tips
Clinicians typically check serum potassium, sodium, creatinine, and fasting glucose within the first few weeks of starting therapy, then periodically thereafter. If potassium drops, a clinician may consider adding a potassiumsparing diuretic (like spironolactone) or recommending dietary changes.
Managing Hypokalemia
Simple diet tweaksthink bananas, orange juice, leafy greenscan add a modest potassium boost. For more stubborn cases, a clinician may prescribe a potassium supplement. Always consult a clinician before making changes to medication or supplement routines.
Contraindications & Interactions
Absolute Contraindications
- Anuria (no urine output).
- Known hypersensitivity to thiazide or sulfonamide structures.
Relative Contraindications
- Severe renal insufficiency.
- Active gout or uncontrolled hyperuricemia.
- Unstable diabetes mellitus.
Key Drug Interactions
- NSAIDs can blunt the diuretic effect.
- Lithium thiazides raise lithium levels, risking toxicity.
- ACE inhibitors/ARBs additive potassium rise; monitor closely.
Interaction Summary
| Drug | Interaction | Clinical Action |
|---|---|---|
| NSAIDs | Reduced diuretic efficacy | Use lowest effective NSAID dose or consider alternative analgesics, as advised by a clinician. |
| Lithium | Elevated lithium serum levels | Monitor lithium levels; adjust dose if needed, under medical supervision. |
| ACEi / ARB | Potassium elevation | Check potassium and renal function regularly. |
EvidenceBased Comparison: Thiazide vs. ThiazideLike
Large trials such as ALLHAT (Antihypertensive and LipidLowering Treatment to Prevent Heart Attack Trial) and SHEP (Systolic Hypertension in the Elderly Program) have shaped our understanding of these drugs.
Cardiovascular Outcomes
Both pure thiazides and thiazidelike agents lower the risk of stroke, myocardial infarction, and heart failure. However, chlorthalidone (a thiazidelike) consistently shows a slightly larger absolute risk reduction in some studies, likely due to its longer halflife and greater potency.
BloodPressure Lowering Potency
Metaanalyses reveal that chlorthalidone can achieve a greater systolic drop compared with an equivalent dose of hydrochlorothiazide in some contexts. That difference grows more evident in resistant hypertension.
SideEffect Profile
Because thiazidelike agents linger longer in the system, they sometimes cause more pronounced electrolyte shifts, especially hypokalemia. Conversely, the shorteracting pure thiazides may be easier to manage in patients prone to dehydration.
Summary of Evidence
| Outcome | Pure Thiazide (e.g., HCTZ) | ThiazideLike (e.g., Chlorthalidone) |
|---|---|---|
| Systolic BP Reduction | Variable (study dependent) | Variable (study dependent) |
| Stroke Risk Reduction | Observed in trials | Observed in trials |
| Hypokalemia Risk | Present | Present |
For a deeper dive into the data, a recent review in the American Journal of Hypertension summarizes these findings.
Putting It All Together
Understanding thiazide diuretics classification isnt just an academic exercise; it directly influences how safely and effectively you (or a loved one) manage high blood pressure or fluid retention under medical care. Remember these takeaways:
- Know the family: Pure thiazides and thiazidelike agents share a mechanism but differ in chemistry, duration, and potency.
- Match the drug to the patient: Elderly, renalimpaired, or goutprone individuals may benefit from a lower dose or a pure thiazide with a shorter halflife, as determined by a clinician.
- Watch electrolytes: Regular labs are the best guard against hidden potassium or sodium swings.
- Talk to your clinician: If youre unsure whether a thiazidelike agent like chlorthalidone is right for you, ask for a riskbenefit discussion with your healthcare provider.
Conclusion
Thiazide diuretics classification is a gateway to smarter, safer bloodpressure and edema management. By distinguishing pure thiazides from thiazidelike drugs, grasping their mechanism of action, and staying vigilant about dosing and side effects, you empower yourself to make informed health decisions. Always keep the conversation open with your healthcare providerafter all, the best treatment plan is the one you both trust and understand. If youve ever tried a thiazide or are considering one, share your experience or questions with your doctor; together you can navigate this essential part of cardiovascular care with confidence.








