



Not medical advice — written by Ngoc Vietsmall, who is not a healthcare professional.
This article summarises publicly available medical information for general readers. It cannot account for your history, medication or symptoms, and it is not a diagnosis or a treatment plan. Any dose mentioned comes from published labelling or guidelines — only your own prescriber can decide what is right for you.
Always speak to a doctor or pharmacist before starting, stopping or changing any treatment. If symptoms are severe or getting worse, seek urgent care. Full disclaimer · How this is written
Thinking about a lung biopsy can feel like standing at the edge of a cliffexciting because it may finally give answers, but scary because the drop could be dangerous. The short answer? Death after a lung biopsy is rarearound 12% for planned procedures, but the risk rises steeply for emergency surgeries.
Below well walk through the numbers, the most common complications, whos most at risk, and practical steps you and your doctor can take to keep the danger as low as possible. Grab a cup of tea, settle in, and lets talk this through like friends.
Quick Mortality Snapshot
What is the overall lung biopsy death rate?
Across large U.S. and European registries the lung biopsy death rate sits at roughly 1.7% for elective (planned) procedures. When the same operation is performed on a patient whos already in critical conditionthink massive bleeding or severe respiratory failurethat number can climb to about 18%. Those figures come from a 2025 analysis of hospital discharge data that examined over 12,000 biopsies.
How does mortality differ by biopsy type?
| Biopsy Type | Reported Death Rate* | Typical Setting |
|---|---|---|
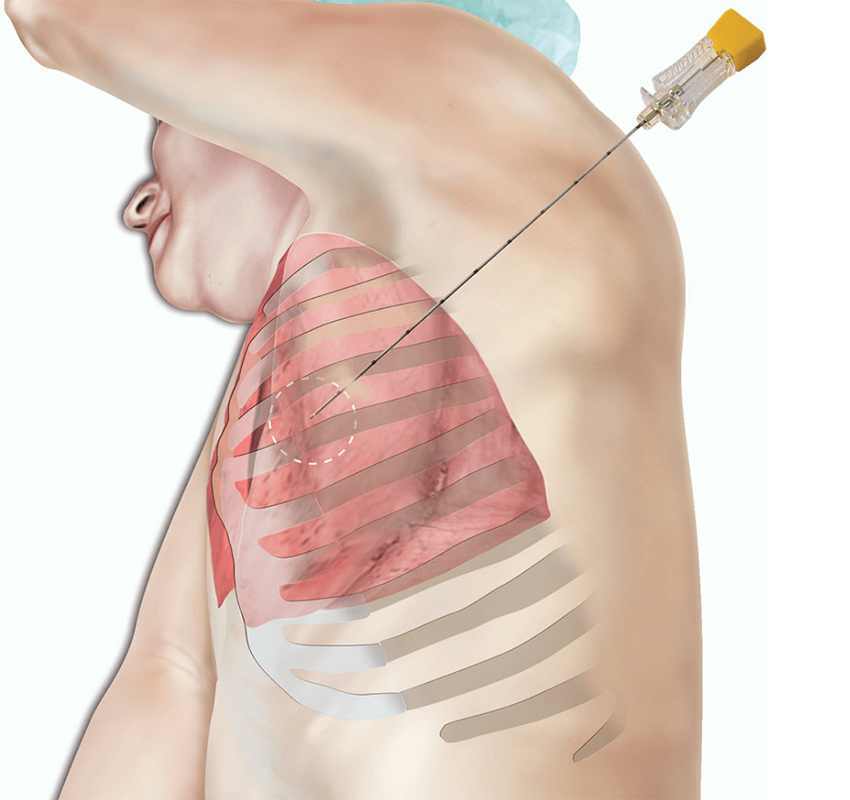
| Surgical (open or VATS) | 1.52% | Elective or diagnostic |
| Percutaneous needle (CTguided) | 0.51% | Outpatient |
| Bronchoscopyguided | <0.1% | Routine |
*Sources: peerreviewed studies in *Annals of Thoracic Surgery* (2017) and *Chest* (2024).
What are the most common fatal complications?
The deadly side of a lung biopsy usually stems from one of three problems:
- Pulmonary hemorrhage that overwhelms the airway (massive hemoptysis).
- Air embolism, where air bubbles travel to the brain or heart.
- Large pneumothorax or hemothorax that collapses the lung and blocks breathing.
These complications are rare, but when they happen they can be swift and severe. A 2024 case series in *Chest* highlighted that most deaths occurred within the first six hours after the procedure, underscoring the importance of close monitoring.
Common Complications
What complications happen most often (nonfatal)?
Even when a biopsy doesnt lead to death, patients frequently experience issues that feel uncomfortable or alarming. The two biggest culprits are:
- Pneumothorax air leaks into the space around the lung in about 1015% of cases. Most resolve on their own, but roughly onethird need a chest tube.
- Minor bleeding seen in 58% of procedures, usually controlled with simple pressure or a brief observation period.
Pneumothorax how often and how its managed
CTguided needle biopsies have a slightly higher pneumothorax rate (around 15%) compared with bronchoscopic approaches (<5%). Most hospitals will do a followup chest Xray an hour after the biopsy. If the lung looks only a little deflated, theyll watch it; if it looks big, theyll insert a small chest tube to let the air out.
How dangerous is a lung biopsy for the elderly?
Age mattersa lot. Patients 70years and older face about double the mortality risk (3%) compared with younger adults. The biggest drivers are coexisting conditions like COPD, heart disease, and reduced lung reserve. One study in the *American Thoracic Society* journal showed that each additional decade of life adds roughly a 0.3% increase in death odds.
Realworld case vignette
Meet Bob, a 78yearold retired teacher who was scheduled for a CTguided biopsy after an incidental nodule showed up on his scan. The team paused his aspirin, gave him a short course of steroids for his COPD, and performed the biopsy with realtime CT guidance. A tiny pneumothorax appeared, but a brief observation period was enoughno chest tube needed, and Bob went home the next day. His story shows that with careful planning, even seniors can navigate the risks safely.
Can a lung biopsy cause cancer to spread?
Thats a common fear, especially for patients facing a potential lung cancer diagnosis. The data say the risk of needletrack seedingwhere cancer cells hitch a ride along the biopsy needleis extremely low, under 0.1% in modern series. In practical terms, its not something most doctors worry about when recommending a biopsy.
HighRisk Groups
Patientrelated risk factors
Besides age, several personal health metrics stack the odds:
- Male sex (about 30% higher odds of death).
- High Charlson comorbidity index (3).
- Severe pulmonary hypertension or uncontrolled heart failure.
- Current use of anticoagulants that havent been stopped appropriately.
Procedurerelated risk factors
Not all biopsies are created equal. The biggest procedural red flags are:
- Urgent or nonelective surgerywhen the team is racing against a deteriorating condition.
- Open surgical approach versus percutaneous needle.
- Lack of realtime imaging guidance, which can increase the chance of a miss or a complication.
Comparison table Elective vs. Nonelective
| Feature | Elective | Nonelective |
|---|---|---|
| Mortality | 1.7% | 18% |
| Typical indication | Diagnostic workup | Acute bleed/respiratory failure |
| Average length of stay | 34days | 710days |
| Common complications | Pneumothorax, minor bleed | Massive hemorrhage, respiratory failure |
Balancing Benefits & Risks
Why do doctors still recommend a lung biopsy?
Because the upside can be lifechanging. A precise histopathology result can:
- Confirm or rule out lung cancer, guiding targeted therapy that can add years.
- Identify specific interstitial lung disease patterns, altering medication choices for up to 90% of patients.
- Prevent unnecessary surgery when imaging alone cant provide a definitive answer.
How can you keep the chance of death or serious harm as low as possible?
Think of it as a safety checklist you and your care team run through together:
- Confirm the indication. Ask yourself Do I really need a tissue sample, or can a lessinvasive test suffice?
- Review health history. Bring a list of all meds, especially blood thinners, and discuss any lung or heart conditions.
- Pick the least invasive technique. For many peripheral nodules, a CTguided needle is safer than an operatingroom surgery.
- Plan for postprocedure monitoring. Most centers keep you under observation for at least four hours and repeat a chest Xray to catch a pneumothorax early.
- Ask about emergency protocols. Knowing the teams plan for a bleed or air embolism can turn anxiety into confidence.
Checklist for patients & physicians
Use this quick reference before the day of the biopsy:
- Indication clearly documented?
- Comorbidities scored (Charlson index, pulmonary function tests)?
- Anticoagulants held appropriately (usually 4872hrs)?
- Imaging modality chosen (CTguided, bronchoscopy, VATS) matched to lesion location?
- Postprocedure monitoring plan (observation duration, repeat imaging) in place?
What does the research say?
A 2025 systematic review in *ScienceDirect* found that when these safety steps are followed, the overall mortality for elective lung biopsies drops to under 1%, even in centers that handle highrisk patients. The same review highlighted that multidisciplinary discussionspulmonology, radiology, and thoracic surgery all at the tablecut complication rates by roughly a third.
What You Can Do Right Now
Questions to ask your doctor
Having a conversation ready can make the whole process feel less intimidating. Try asking:
- What is my personal risk of death or serious complications?
- Is there a less invasive alternative that could give us the same information?
- How will you manage anticoagulants before and after the procedure?
- What signs should I watch for once Im home?
- Can we schedule a followup call within 24hours after the biopsy?
How to prepare at home
Good preparation can shave minutes off your recovery and reduce anxiety. Heres a short prebiopsy todo list:
- Stop smoking at least 48hours before, if you smoke.
- Stay hydrateddrink water unless youve been told otherwise.
- Arrange for someone to drive you home; youll likely feel a bit groggy.
- Wear comfortable clothing; loose sleeves make chestwall access easier.
- Write down any questions you have now, so you dont forget them when youre in the exam room.
When youre out of the hospital
Most patients feel fine after a few hours of observation. Still, keep an eye out for these warning signs:
- Sudden sharp chest pain or worsening shortness of breath.
- A rapid drop in oxygen saturation (if you have a pulse oximeter at home).
- Bleeding from the biopsy site that doesnt stop with gentle pressure.
- Fever or chillsthese could signal infection.
If any of these occur, call your surgeon or head to the nearest emergency department. A quick chest Xray can tell you if a delayed pneumothorax is developing.
Helpful Resources & Further Reading
For those who love to dive into the data, the American Thoracic Society biopsy guidelines offer a thorough, evidencebased rundown of indications, technique selection, and postprocedure care. Another concise review of complication rates can be found in a recent PubMed study on percutaneous lung biopsies, which breaks down mortality by age and comorbidity groups.
Conclusion
In the end, a lung biopsy is a powerful tool that can unlock the mystery behind a shadow on an Xray, but it isnt without risk. The lung biopsy death rate sits under 2% for planned procedures, climbing sharply when urgency and poor health intersect. Most complicationspneumothorax, minor bleedingare manageable with vigilant monitoring and a solid care plan.
Understanding whos most vulnerable (the elderly, those with multiple health issues) and what steps can shrink the danger (preprocedure optimization, choosing the least invasive technique, and postprocedure observation) puts you in the drivers seat. Talk openly with your medical team, ask the right questions, and use the checklist weve laid out. If you feel informed and supported, the odds tilt in your favor.
Weve shared the facts, the numbers, the anecdotes, and the practical tipsnow its your turn. What concerns do you have about a lung biopsy? Have you or a loved one gone through one? Share your thoughts, and lets keep the conversation going. Knowledge is the best medicine, after all.








