



Not medical advice — written by Ngoc Vietsmall, who is not a healthcare professional.
This article summarises publicly available medical information for general readers. It cannot account for your history, medication or symptoms, and it is not a diagnosis or a treatment plan. Any dose mentioned comes from published labelling or guidelines — only your own prescriber can decide what is right for you.
Always speak to a doctor or pharmacist before starting, stopping or changing any treatment. If symptoms are severe or getting worse, seek urgent care. Full disclaimer · How this is written
Quick Answer Summary
Yes, autoimmune progesterone dermatitis (APD) can be dangerous, but most cases are mild and manageable. The condition ranges from itchy, cyclical rashes that disappear with your period to rare, severe reactions that require emergency care. Knowing the signs, triggers, and treatment options empowers you to stay safe and keep the flareups under control.
What Is APD?
Definition & How It Works
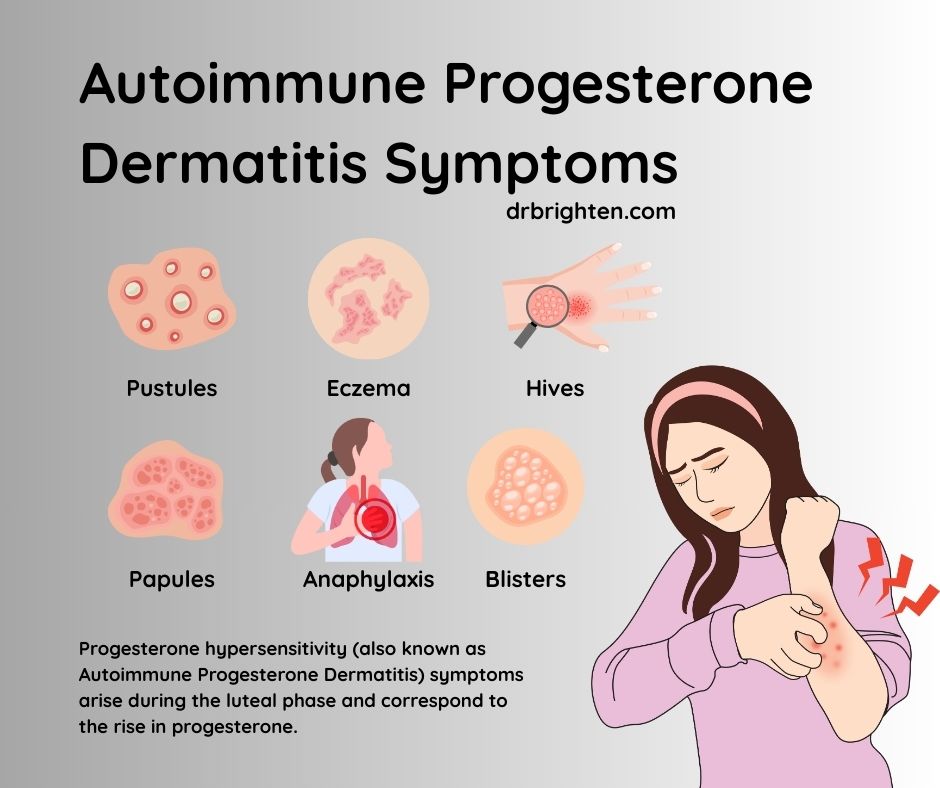
APD is a rare, hormonedriven skin reaction where your immune system mistakenly attacks your own progesterone. Progesterone peaks during the luteal phase of your menstrual cycle, so the rash typically appears a week or two before menstruation and fades when hormone levels drop.
Who Gets It?
It mostly affects women of reproductive agethink late teens to early 40s. Researchers estimate the condition is how rare is autoimmune progesterone dermatitis? at roughly 1 in 20,000 to 1 in 100,000 women, though exact numbers are fuzzy because many cases go undiagnosed.
RealWorld Example
Take Mayas story: she first noticed a persistent hiveslike rash that flared each month just before her period. After months of doctor hops, a dermatologist performed a progesterone skin test and confirmed APD. With targeted treatment, Mayas flareups dropped from weekly to onceinawhile occurrences.
How Dangerous Is APD?
Spectrum of Severity
Most women experience mildtomoderate symptomsred patches, itching, or eczemalike plaques that respond to topical steroids. A small minority develop severe reactions such as extensive erythema multiforme, StevensJohnsonlike skin loss, or even anaphylaxis. According to a review in Medical Journal (PMCID3423662), severe cases are uncommon but demand immediate medical attention.
Red Flags When to Call 911
- Sudden swelling of the face, lips, or tongue
- Difficulty breathing or wheezing
- Rapid drop in blood pressure (feeling faint)
- Widespread blistering or skin peeling
If any of these pop up, treat it like an emergency. Even though most APD flares are not lifethreatening, those rare severe reactions can be.
Expert Insight
Dr. Elena Ruiz, a boardcertified dermatologist, says, While APD is rarely fatal, the emotional toll of unpredictable skin eruptions can be significant. Early recognition and a solid treatment plan make all the difference.
Symptoms By Cycle
Early Warning Signs
Two to three days before your period, you might notice a subtle itch or a faint flushing on your chest or arms. Its easy to brush off as just premenstrual skin changes, but if its recurring month after month, take note.
PeakPhase Symptoms
When progesterone hits its highest point (about 710 days before menstruation), the rash can intensify:
- Urticaria (hives) that come and go
- Eczematous plaques that feel rough and dry
- Folliculitis (tiny red bumps around hair follicles)
- Burning or stinging sensations, especially on the neck, back, or abdomen
Visual Aid
Seeing helps there are plenty of progesterone rash pictures online that illustrate the typical presentation. Look for the cyclical pattern rather than a oneoff rash.
Diagnosis Guide Overview
Clinical Evaluation
The first step is a detailed interview. Your doctor will ask you to keep a rash calendar for a few cycles, noting when the rash appears, its shape, and any accompanying symptoms. That diary is gold for confirming a hormonal link.
Tests & Procedures
1. Intradermal progesterone challenge a tiny amount of progesterone is injected into the skin. A positive reaction (redness or swelling within 30 minutes) supports the diagnosis.
2. Serum progesterone levels usually drawn at the luteal phase to see if levels correlate with flare intensity.
3. Skin biopsy (optional) helps rule out other conditions.
Differential Diagnosis Checklist
| Condition | Key Difference |
|---|---|
| Allergic contact dermatitis | No menstrual cycle pattern; triggered by external substances. |
| Lupus flare | Positive ANA test, systemic joint pain, photosensitivity. |
| Hormonal acne | Comedones and cystic lesions, not eczematous plaques. |
Treatment Options Overview
Conventional Medical Therapy
Most physicians start with the simplest approach:
- Topical steroids apply at the first sign of a rash for rapid itch relief.
- Oral antihistamines especially secondgeneration options (e.g., cetirizine) that calm hives without causing drowsiness.
- Hormonal suppression combined oral contraceptives, progesteronefree pills, or GnRH agonists can flatten the hormonal rollercoaster. Discuss risks, like potential weight changes, with your doctor.
Natural & Lifestyle Strategies
If you prefer a gentler route, consider these evidencebased tweaks (theyre not a replacement for medical care, but they can complement it):
- Autoimmune progesterone dermatitis foods to avoid: limit highhistamine foods (aged cheese, fermented soy), dairy, and excessive caffeine, as they may amplify inflammation.
- Stress management: yoga, meditation, or a simple 10minute breathing exercise each morning can calm the hormonal axis.
- Sleep hygiene: aim for 79 hours; erratic sleep can surge cortisol, which in turn may worsen skin flares.
StepbyStep Management Plan
- Track your rash with a calendar or phone app.
- At the first hint of itching, apply a lowpotency topical steroid.
- If the rash persists beyond 48hours, add an oral antihistamine.
- Schedule a followup with a dermatologist to discuss hormonal suppression if flares become frequent.
Surgical Intervention (Last Resort)
In the most refractory caseswhen medication fails and quality of life plummetssome specialists consider bilateral oophorectomy (removal of the ovaries). This is a major surgery with permanent menopause, so its rarely chosen and only after exhaustive medical therapy.
Pregnancy & Fertility
Can I Get Pregnant With APD?
Absolutely. Many women with APD have healthy pregnancies. The key is close monitoring because progesterone naturally rises during pregnancy, which can intensify skin symptoms. A collaborative team of a dermatologist, obstetrician, and possibly an allergist is ideal.
Managing APD During Pregnancy
Safe medication options include lowdose systemic steroids and secondgeneration antihistamines (both have solid safety data in pregnancy). Hormonal suppressors like oral contraceptives are offlimits, so a dermatologist may pivot to topical treatments and lifestyle tweaks.
Patient Story
Laura, now a mother of two, recounts: My first trimester was rough, but my doctor switched me to a gentle steroid cream and a pregnancysafe antihistamine. The rash stayed mild, and I delivered a healthy baby. Her experience underscores that proactive care makes a huge difference.
Weight Gain Impact
Does APD Cause Weight Gain?
The disease itself doesnt directly add pounds. However, some treatmentsespecially certain hormonal contraceptives or highdose steroidscan lead to modest weight increase. Its a tradeoff: controlling the rash versus a few extra ounces.
LongTerm Effects & Quality of Life
Uncontrolled flares may cause skin thickening, scarring, or pigment changes, which can affect confidence. Incorporating scarreduction creams (containing silicone) and counseling can help mitigate emotional distress.
Bottom Line Summary
Autoimmune progesterone dermatitis can be dangerous, especially in its severe form, but for the vast majority its a manageable, cyclical skin condition. Early detection, diligent symptom tracking, and a partnership with a knowledgeable dermatologist are your strongest allies. Whether you opt for topical steroids, antihistamines, hormonal therapy, or natural lifestyle tweaks, the goal is the same: keep the rash from stealing your peace of mind.
If you recognize any of the patterns described here, consider starting a rash diary today and reaching out to a healthcare professional. And rememberyoure not alone on this journey. Share your story, ask questions, and lets support each other toward clearer skin and calmer days.








