



Not medical advice — written by Ngoc Vietsmall, who is not a healthcare professional.
This article summarises publicly available medical information for general readers. It cannot account for your history, medication or symptoms, and it is not a diagnosis or a treatment plan. Any dose mentioned comes from published labelling or guidelines — only your own prescriber can decide what is right for you.
Always speak to a doctor or pharmacist before starting, stopping or changing any treatment. If symptoms are severe or getting worse, seek urgent care. Full disclaimer · How this is written
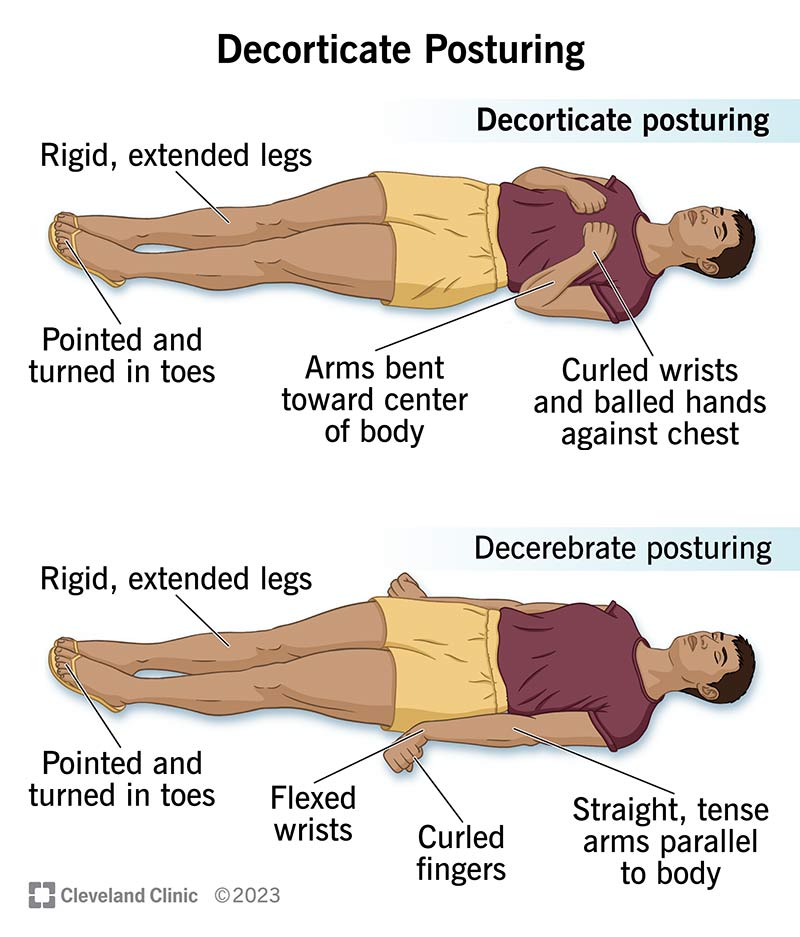
Hey there, lets cut straight to the chase. If youre reading this, youve probably seen the terms decerebrate and decorticate tossed around after a head injury and wondered what on earth they mean, which one is more serious, and what it all means for the person affected. In a nutshell, decorticate posturing shows the arms curled in like a hug, while decerebrate posturing leaves the limbs stiff and straightened. The latter usually signals deeper brain damage and a tougher road ahead.
Quick Answers
What is decerebrate vs decorticate posturing? Both are abnormal body positions that appear when the brain cant properly control muscle tone after a severe injury. Decorticate = flexed arms, clenched fists; decerebrate = extended arms, rigid legs.
Which one is worse? Decerebrate posturing is generally considered worse because it points to damage in the brainsteman area that regulates breathing, heart rate, and consciousness. Decorticate indicates injury higher up the brain, which often has a better prognosis.
What They Look Like
Decorticate Posturing: The BentArm Sign
Picture someone with their elbows sharply bent, forearms flexed toward the chest, and fists tightly clenched. Their legs may be extended or slightly flexed at the knees. This pattern shows the corticospinal tract (the main highway for voluntary movement) has been disrupted above the brainstem.
Mnemonic to Remember
Think CORTICAl Curls. The word curls reminds you of the curledup arms in decorticate posturing.
Decerebrate Posturing: The StraightArm Sign
Now imagine a body thats completely straightarms and legs locked in extension, wrists flexed, and possibly the head arching backward. This rigid pose indicates the injury has swept down to the brainstem, specifically the midbrain or pons.
Mnemonic to Remember
Picture BRainstem BRoadStretched. Broadstretched gives you the image of fully extended limbs.
Why One Is Worse
Neurological Level of Injury
Decerebrate posturing signals that the damage has reached the brainstema critical hub for lifesupporting functions. Decorticate signals a lesion higher up, in the cerebral cortex or internal capsule. Because the brainstem controls essential autonomic processes, any compromise there often leads to a lower chance of recovery.
Survival & Prognosis Data
Studies from the Cleveland Clinic show that patients with decerebrate posturing have a markedly lower survival rateoften under 30%whereas those who exhibit decorticate posturing may have survival rates ranging from 40% to 60%, depending on the severity of the injury and the speed of medical intervention.
Clinical Implications
When you spot decerebrate posturing, emergency teams move fast to secure the airway, lower intracranial pressure (ICP), and consider neurosurgical decompression. Decorticate posturing still demands urgent care, but the treatment pathway can be slightly less aggressive because the brainstem is still intact.
Root Causes
What Causes Decorticate Posturing?
Typical culprits include severe traumatic brain injury (TBI), large intracranial hemorrhages (like a subdural hematoma), or massive strokes that crush the internal capsule. The common thread is damage to the corticospinal tract before it reaches the brainstem.
Quick Checklist for First Responders
- Flexed elbows
- Clenched fists
- Legs possibly flexed at the knees
What Causes Decerebrate Posturing?
This posture usually follows brainstem compression, severe hypoxia (lack of oxygen), or herniation where brain tissue is forced through the skulls openings. Anything that crushes the midbrain or pons can trigger this response.
Quick Checklist for First Responders
- Arms fully extended
- Wrists flexed (hands pointing downward)
- Legs rigid and straight
RealTime Differentiation
Physical Examination Steps
First, observe the patients natural posture. Then, apply a painful stimulus (like a nailbed pinch) to see if the response changessometimes a flexor response can mask the underlying pattern. Note the tone of each limb and the direction of the arms and legs.
SidebySide Comparison Table
| Feature | Decorticate | Decerebrate |
|---|---|---|
| Arm position | Flexed at elbows | Extended |
| Hand position | Clenched, pronated | Wrists flexed, hands pointing down |
| Leg position | Extended, may be flexed at knees | Fully extended |
| Brain area affected | Corticospinal tract (above brainstem) | Brainstem (midbrain/pons) |
| Prognosis | Better | Worse |
Imaging Correlates
CT scans can quickly reveal midline shifts, hematomas, or brain swelling that match the clinical picture. MRI offers a more detailed view of the corticospinal tract and brainstem integrity, but its usually done after the patient is stabilized.
Expert Insight
According to a recent review in StatPearls, CT remains the firstline imaging tool for identifying lesions that cause abnormal posturing, while MRI helps differentiate between permanent tract damage and reversible edema.
Treatment Pathways
Immediate Emergency Management
Time is everything. The first steps are securing the airway (often with intubation), delivering 100% oxygen, and administering hypertonic saline or mannitol to lower ICP. Medications like barbiturates may be used to calm the brains electrical storm.
Medication Overview
- Mannitol: pulls fluid out of the brain.
- Hypertonic saline: restores osmotic balance.
- Barbiturates: suppresses neuronal activity when ICP is dangerously high.
LongTerm Rehabilitation Outlook
Surviving the acute phase is just the beginning. Physical therapy, occupational therapy, and speech-language pathology become crucial. Patients who initially presented with decorticate posturing often regain meaningful function with intensive rehab, while those with decerebrate posturing may require more supportive care and, in some cases, longterm ventilatory support.
RealWorld Success Stories
One 28yearold motorcyclist arrived at the ER with decorticate posturing after a highspeed crash. Thanks to rapid surgical decompression and a 12month rehab program, he now walks with a cane and lives independently. Stories like this remind us that early, accurate recognition can change lives.
Bottom Line
Understanding decerebrate vs decorticate posturing isnt just academicits a lifesaving skill. Decorticate (bentarm) posturing points to injury above the brainstem and usually carries a better prognosis. Decerebrate (straightarm) posturing signals brainstem involvement, meaning higher risk and a lower survival rate. By learning to spot these cues, you help clinicians act faster, set realistic expectations for families, and, ultimately, improve outcomes.
If you found this guide helpful, feel free to share it with anyone caring for a loved one whos faced a traumatic brain injury. Knowledge, after all, is one of the strongest tools we have in the fight for recovery.








