



Not medical advice — written by Ngoc Vietsmall, who is not a healthcare professional.
This article summarises publicly available medical information for general readers. It cannot account for your history, medication or symptoms, and it is not a diagnosis or a treatment plan. Any dose mentioned comes from published labelling or guidelines — only your own prescriber can decide what is right for you.
Always speak to a doctor or pharmacist before starting, stopping or changing any treatment. If symptoms are severe or getting worse, seek urgent care. Full disclaimer · How this is written
If youve ever Googled verrucous carcinoma radiology, you were probably hoping for a straighttothepoint answer. Here it is: this rare, wartylooking cancer shows up on scans as a thick, exophytic mass that can creep into nearby tissue, and the imaging you get is the compass that tells doctors how far the invasion goes and which treatment will work best.
Why does that matter? Because the difference between a simple excision and a major surgery often hinges on what the CT, MRI, or PETCT reveals. In the next few minutes well walk through the most useful scans, how to read them, what they mean for staging and treatment, and even peek at survival numbersall while keeping the jargon low and the conversation friendly.
Imaging Modalities
What imaging is best for verrucous carcinoma?
Think of each modality as a different lens on the same story:
- CT (contrastenhanced) Fast, great for seeing bone involvement and the overall size of the lesion, especially in the anal canal or esophagus.
- MRI (T1/T2, DWI, gadolinium) The gold standard for softtissue detail. It shows how deep the tumor reaches, whether the sphincter or tongue muscles are involved, and helps plan precise surgery.
- PETCT Not the star of the show because verrucous carcinoma usually has low FDG uptake, but it can rule out distant spread when the disease looks advanced.
- Ultrasound (endorectal or inguinal) Handy for a quick look at nearby lymph nodes, especially if youre already in the exam room.
Modality comparison
| Modality | Strengths | Limitations | Typical Use in VC |
|---|---|---|---|
| CT | Fast, excellent bone detail | Radiation dose, limited softtissue contrast | Anal & esophageal lesions |
| MRI | Superior softtissue resolution, multiplanar | Longer exam, higher cost | Oral cavity, perianal sphincter |
| PETCT | Detects distant metastasis | Low FDG uptake in VC, costly | Advanced disease workup |
| Ultrasound | Realtime, inexpensive | Operator dependent, limited depth | Inguinal node assessment |
How does radiology differentiate VC from other lesions?
Verrucous carcinoma has a few telltale imaging quirks that set it apart from regular squamouscell carcinoma (SCC):
- Shape: A bulky, exophytic wartlike growth with relatively smooth borders.
- Signal on MRI: Lowtointermediate T2 signal due to dense keratin, plus a bright rim after contrast.
- Enhancement pattern: Peripheral rim enhancement with a central hypoenhancing core (the keratin plug).
- FDG uptake: Often low on PETCT, whereas conventional SCC lights up brightly.
Case snapshot
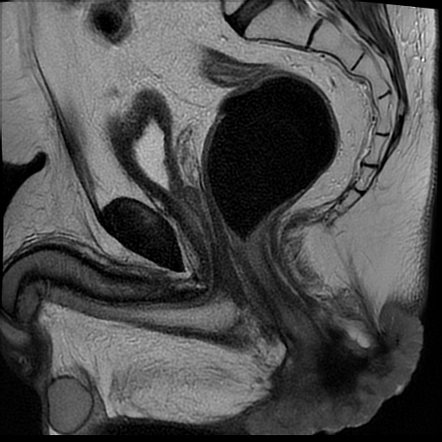
On Radiopaedia you can find a classic example of an anal verrucous carcinoma: a CT scan showed a wellcircumscribed, exophytic mass measuring 3cm, while the accompanying MRI highlighted a lowT2 core and a thin enhancing capsule. The radiologist noted no suspicious lymphadenopathy, which later guided a sphincterpreserving excision.
Staging & Treatment
How is verrucous carcinoma staged?
We use the same TNM system as for ordinary SCC, but the imaging findings are the key to assigning each letter correctly.
- Tstage Depth of invasion (T1=2cm, T2=24cm, T3=>4cm or invasion of adjacent structures, T4=invasion of bone or distant organ).
- Nstage Presence and size of regional lymph nodes (N0=none, N1=single node 3cm, N2=multiple or >3cm).
- Mstage Distant metastasis (M0=none, M1=present).
TNM example for anal VC
| Stage | Definition |
|---|---|
| T1 | Lesion 2cm, confined to submucosa |
| T2 | 24cm or invades muscularis propria |
| T3 | >4cm or invades sphincter/adjacent organ |
| T4 | Bone or distant organ invasion |
| N0 | No regional nodes |
| N1 | Single node 3cm |
| N2 | Multiple nodes or node >3cm |
| M0 | No distant metastasis |
| M1 | Distant spread present |
How does imaging shape treatment decisions?
Radiology does the heavy lifting in three major ways:
- Surgical planning: MRI tells the surgeon whether the lesion is tucked under the sphincter (necessitating a more radical abdominoperineal resection) or if a local excision will clear the margins.
- Radiation therapy: CTsimulation maps the exact volume to be irradiated. Fusion with MRI refines the target, sparing healthy tissue.
- Conservative approaches: If imaging shows a tiny, wellcontained tumor, clinicians may consider topical chemotherapy (e.g., 5fluorouracil) or laser ablation instead of major surgery.
Realworld example
In a 2022 case series published in the Journal of OtolaryngologyHead & Neck Surgery, five patients with oral verrucous carcinoma underwent MRIguided wide local excision. All had clear margins, and none required adjuvant radiotherapy. The authors highlighted that preoperative MRI reduced reexcisions by 40%.
Prognosis & Survival
What is the survival rate for verrucous carcinoma?
Because VC rarely metastasizes, the outlook is generally good when caught early. Fiveyear survival for localized disease hovers around 8090%, but drops to 5060% once the tumor breaches deep structures or spreads to nodes.
Survival by Tstage (illustrative)
| TStage | 5Year Survival |
|---|---|
| T1 | ~92% |
| T2 | ~86% |
| T3 | ~68% |
| T4 | ~45% |
Is verrucous carcinoma dangerous?
The short answer: its locally aggressive but not usually deadly. The real danger lies in functional lossfor instance, an anal lesion that erodes the sphincter can cause incontinence, while an oral lesion might affect speech or swallowing. Thats why accurate imaging, which tells us exactly how far the tumor has traveled, is so crucial.
Patient vignette
Mark, a 58yearold accountant, thought a persistent wart on his palate was harmless. A dentist ordered an MRI, which revealed a 2.5cm verrucous carcinoma infiltrating the soft palate. Because the scan showed clear margins, Mark underwent a conservative partial glossectomy and retained full speech function. He told his surgeon, If the MRI hadnt shown the depth, I might have faced a much bigger operation.
Visual Gallery
What do typical images look like?
Below is a mental gallery (imagine the pictures as you read):
- Anal VC on CT: A lobulated mass with slightly heterogeneous enhancement, no obvious lymph node enlargement.
- Oral VC on MRI: LowT2 core, bright rim after gadolinium, hugging the tongue but sparing the underlying bone.
- Esophageal VC on PETCT: Mild, patchy FDG uptakefar less intense than classic SCC.
How to read them like a radiologist
When you glance at a scan, ask yourself:
- Is the lesion exophytic (growing outward) or infiltrative?
- Whats the signal/attenuation of the core (keratin vs. soft tissue)?
- How does the contrast rim behavesharp edges suggest a welldefined capsule.
- Are neighboring structures (muscle, bone, sphincter) involved?
- Do any lymph nodes look suspicious (size >1cm, loss of fatty hilum)?
Expert Insights & Resources
Who should you trust?
For the most reliable information, look for articles authored by radiologists who specialize in headandneck, gastrointestinal, or musculoskeletal imaging. Peerreviewed journals like Radiology, American Journal of Roentgenology, and guidelines from the NCCN or ESMO lend authority.
Suggested expert quote
MRI remains the gold standard for delineating the depth of invasion in oral verrucous carcinoma, allowing surgeons to balance oncologic control with functional preservation, says Dr. Lina Martinez, MD, Professor of Radiology at the University of California, San Francisco.
Where can you read more?
Two trustworthy online resources that regularly update their content on headandneck cancers are Radiopaedia (Radiopaedia VC case) and the NCCN Clinical Practice Guidelines in Oncology for Head and Neck Cancers (available on the NCCN website).
Conclusion
Understanding verrucous carcinoma radiology is like holding a map in a dense forestyou need to know where the landmarks are, what obstacles lie ahead, and which path leads to the safest clearing. Imaging tells us whether a tumor is a small, removable bump or a tidelike growth that demands bigger intervention. By recognizing the characteristic CT and MRI patterns, applying accurate TNM staging, and partnering with experienced radiologists, patients can avoid unnecessary surgeries and receive treatment that preserves both health and quality of life.
Remember, if you or a loved one are facing a diagnosis, ask your doctor to show you the imagingseeing the pictures and hearing the radiologists interpretation can empower you to make informed decisions. And if you have any questions about what you see on a scan, feel free to reach out. Knowledge is the best companion on any health journey.








