



Not medical advice — written by Ngoc Vietsmall, who is not a healthcare professional.
This article summarises publicly available medical information for general readers. It cannot account for your history, medication or symptoms, and it is not a diagnosis or a treatment plan. Any dose mentioned comes from published labelling or guidelines — only your own prescriber can decide what is right for you.
Always speak to a doctor or pharmacist before starting, stopping or changing any treatment. If symptoms are severe or getting worse, seek urgent care. Full disclaimer · How this is written
Let’s cut to the chase: a single episode of paroxysmal atrial fibrillation (PAF) can feel like a harmless flutter, but it can also be a warning sign that your heart is trying to tell you something serious. The good news? With the right knowledge, you can spot the red flags, manage the triggers, and keep the risk of stroke or heart failure under control.
What Is Paroxysmal AF?
Definition and key characteristics
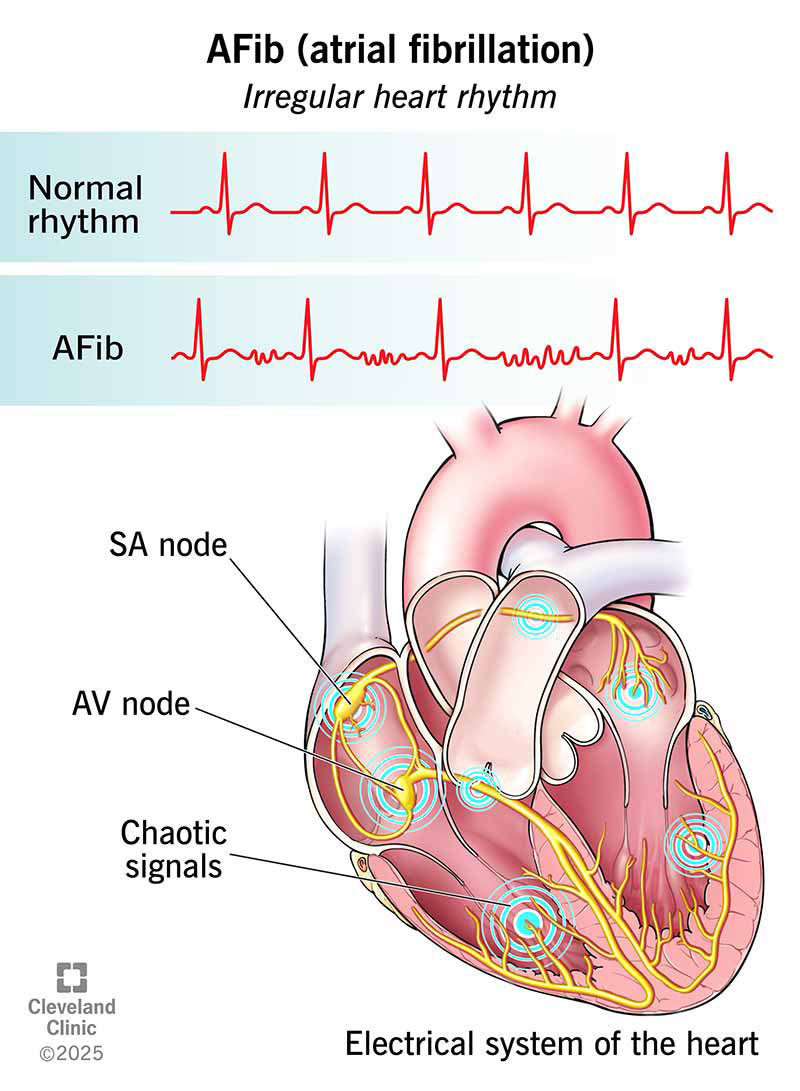
Paroxysmal atrial fibrillation is a type of irregular heartbeat that starts suddenly and usually stops on its own within seven days—often in a matter of minutes or hours. During an episode, the upper chambers of the heart (the atria) beat chaotically instead of in a coordinated rhythm, which can make you feel palpitations, light‑headedness, or even nothing at all.
How it differs from persistent & permanent AFib
Think of AFib as a spectrum. At one end you have paroxysmal—the brief, “come‑and‑go” episodes. In the middle sits persistent AF, which lasts longer than a week or requires medical intervention to stop. At the far end is permanent AF, where the irregular rhythm won’t convert back to normal, even with treatment.
Comparison Table
| Type | Typical Episode Length | Spontaneous Conversion? | Long‑Term Risk Profile |
|---|---|---|---|
| Paroxysmal | Seconds to < 7 days | Yes, often within minutes | Elevated stroke risk; manageable with treatment |
| Persistent | > 7 days | Requires medication or cardioversion | Higher risk of heart‑failure, stroke |
| Permanent | Continuous | Rarely reverts | Highest long‑term complications |
Typical episode length & spontaneous conversion
Most people experience an episode that resolves in less than 24 hours. However, even these short bursts can lead to blood clots forming in the atria—tiny troublemakers that may travel to the brain and cause a stroke. That’s why doctors treat PAF seriously, even when it feels “just a flutter.”
How Serious Can It Be?
Immediate health risks
While PAF often feels benign, the immediate risks are real. The irregular rhythm can cause a dangerously fast heart rate, sometimes exceeding 150 beats per minute—a threshold many cardiologists consider a dangerous heart rate with AFib. A rapid rate reduces the heart’s ability to pump blood efficiently, potentially leading to chest pain, shortness of breath, or fainting.
When a “self‑terminating” episode is still dangerous
Even if the episode stops on its own, the chaotic atrial activity may have already sent a clot into the bloodstream. According to a study published in the BMJ, patients with untreated paroxysmal AF have a stroke risk roughly five times higher than those without AF. That’s why many clinicians recommend anticoagulation therapy after the first documented episode, especially if you have other risk factors like high blood pressure or diabetes.
Long‑term consequences if left untreated
If PAF is repeatedly ignored, it can evolve into persistent or permanent AF, which dramatically raises the risk of heart failure and reduces overall life expectancy. The American Heart Association notes that regular AF can cut life expectancy by several years, depending on age and comorbidities.
Real‑World Case Vignette
Meet Laura, a 58‑year‑old teacher who brushed off a two‑hour flutter as “just stress.” Six months later, she suffered a mild stroke. Imaging revealed a clot that had likely formed during an unnoticed PAF episode. After the event, Laura began anticoagulation and a rhythm‑control plan, and she’s now stroke‑free for two years. Her story reminds us that “nothing felt wrong” isn’t always a clean bill of health.
What Triggers Paroxysmal AF?
Cardiac triggers
Underlying heart conditions—like coronary artery disease, heart valve problems, or a history of heart failure—can spark PAF. Damaged heart tissue creates electrical “short‑cuts” that make the atria more prone to erratic firing.
Non‑cardiac triggers
Electrolyte imbalances (especially low potassium or magnesium), thyroid disorders, fever, and infections can all tip the electrical balance. A sudden surge of adrenaline during a panic attack or an intense workout can also push vulnerable hearts over the edge.
Lifestyle & environmental factors
Think of caffeine, alcohol, and smoking as the mischievous side‑kicks that love to stir up trouble. A study from the Cleveland Clinic found that binge drinking raises the odds of a PAF episode by up to 30% in susceptible individuals. Sleep apnea, chronic stress, and even dehydration are other culprits you might not associate with your heart rhythm.
Quick‑Check Checklist
- Do you drink more than two alcoholic drinks a day?
- Is your caffeine intake high (four+ cups of coffee/energy drinks)?
- Do you have untreated high blood pressure or thyroid issues?
- Are you getting at least 7 hours of sleep and managing stress?
- Have you recently been sick, feverish, or overly dehydrated?
When To Seek Emergency Care?
Dangerous heart‑rate thresholds
Most clinicians consider a heart rate above 150 bpm in AFib “dangerously high,” especially if you feel dizzy, chest‑tight, or short‑of‑breath. If you can’t control the rate with your usual medication, it’s time to call emergency services.
Red‑flag symptoms
- Sudden, severe chest pain
- Shortness of breath that worsens quickly
- Fainting or near‑fainting episodes
- Weakness or numbness on one side of the body (possible stroke sign)
- Rapid heart rate that won’t slow down even with rest
Guidelines for ER visits
If any of the above symptoms appear, head to the nearest emergency department. Even if the episode stops, a rapid heart rate can leave lingering clot risk that needs immediate anticoagulation. The American Heart Association recommends that anyone with new‑onset AF and any of these red flags should seek care within the hour.
Decision Flowchart
- Palpitations only → Monitor, record heart rate, call your doctor if >150 bpm.
- Palpitations + chest pain/shortness of breath → Call 911 or go to ER.
- Palpitations + neurological signs (numbness, slurred speech) → Immediate emergency care.
Best Treatments for PAF
Rate‑control vs. rhythm‑control strategies
Rate control aims to keep the heart beating at a safe speed, usually with beta‑blockers or calcium‑channel blockers. Rhythm control attempts to restore normal sinus rhythm, often using anti‑arrhythmic drugs, electrical cardioversion, or catheter ablation.
Medication overview
- Beta‑blockers (e.g., metoprolol) – slow the heart rate.
- Calcium‑channel blockers (e.g., diltiazem) – also slow the rate.
- Anti‑arrhythmics (e.g., flecainide, amiodarone) – aim for rhythm restoration.
- Anticoagulants (e.g., warfarin, apixaban) – prevent clot formation; essential after any documented episode if CHA₂DS₂‑VASc score≥2.
Non‑pharmacologic options
Electrical cardioversion delivers a synchronized shock to reset the heart’s rhythm—often used when medication fails to convert a persistent episode. Catheter ablation, a minimally invasive procedure that isolates the problematic electrical pathways, has become the go‑to for many with recurrent PAF, especially younger patients who want to avoid lifelong medication.
Comparative analysis of treatments
When asked “what is the best treatment for paroxysmal atrial fibrillation?” the answer depends on individual factors—age, symptom burden, comorbidities, and personal preference. In general, early rhythm control (including ablation) shows better quality‑of‑life outcomes, while rate control paired with anticoagulation works well for older patients or those with milder symptoms.
Treatment Comparison Table
| Approach | Success Rate | Key Risks | Typical Candidates |
|---|---|---|---|
| Rate‑control meds | 70‑80% achieve target < 100 bpm | Fatigue, bradycardia | Older patients, mild symptoms |
| Rhythm‑control meds | 60‑70% maintain sinus rhythm | Pro‑arrhythmia, organ toxicity | Younger, symptomatic |
| Cardioversion | 85‑95% immediate conversion | Procedural discomfort, arrhythmia recurrence | Acute episodes, refractory |
| Catheter ablation | 70‑80% long‑term freedom | Pulmonary vein injury, rare stroke | Recurrent PAF, medication‑failed |
Life Expectancy With AF?
Does PAF shorten life expectancy?
On its own, a single paroxysmal episode doesn’t dramatically cut lifespan. However, the cumulative effect of repeated episodes—and especially if they progress to persistent or permanent AF—can increase mortality by 10–20% over a decade, mainly due to stroke and heart‑failure complications.
Impact of effective treatment on prognosis
Studies from the Heart Foundation show that patients on appropriate anticoagulation and who achieve rhythm control have survival rates close to the general population. In other words, treating PAF aggressively can essentially neutralize the life‑expectancy penalty.
PAF vs. general AF life expectancy
When you compare “atrial fibrillation life expectancy” with “paroxysmal atrial fibrillation life expectancy,” the former is generally lower because it includes the entire AF spectrum, encompassing more severe forms. Keeping the condition in the paroxysmal stage—through lifestyle tweaks and early treatment—offers the best odds for a normal lifespan.
Survival Curve (illustrative)
Imagine two lines on a graph: one for well‑managed PAF patients (flat, near‑normal survival) and another for untreated persistent AF (steeper decline). That visual difference underscores how much we can influence outcomes with proper care.
Practical Takeaways & Steps
10‑step self‑care checklist
- Track every episode: date, duration, heart rate.
- Know your CHA₂DS₂‑VASc score; discuss anticoagulation with your doctor.
- Limit alcohol to ≤2 drinks per week; avoid binge drinking.
- Keep caffeine intake moderate (≤2 cups of coffee daily).
- Maintain a balanced diet rich in potassium and magnesium (bananas, leafy greens).
- Exercise regularly but avoid extreme endurance activities without medical clearance.
- Manage stress through meditation, yoga, or simple breathing exercises.
- Get a sleep study if you snore loudly or feel unrested—sleep apnea is a hidden AF trigger.
- Schedule regular follow‑ups to reassess rhythm, rate, and medication side‑effects.
- Know the emergency signs (see “When To Seek Emergency Care?”) and keep a list of emergency contacts handy.
How to discuss PAF with your doctor
Bring a concise log of episodes, list any triggers you suspect, and ask specific questions: “What is the most appropriate anticoagulant for my risk profile?” or “Would catheter ablation improve my quality of life?” Clear communication empowers both you and your clinician to craft a personalized plan.
Resources & support groups
Connecting with others who live with AF can be incredibly reassuring. The American Heart Association offers an online community, while local hospital foundations often host monthly support meetings. Sharing experiences not only reduces anxiety but also provides practical tips you might not hear from a clinician.
Downloadable PDF Checklist
Ready to take action? Click the link below to download a printable version of the self‑care checklist. (You’ll also receive a one‑page guide on when to seek emergency care.)
Download AFib Self‑Care Checklist
Conclusion
Paroxysmal atrial fibrillation can feel like a fleeting buzz, but ignoring it may invite serious complications such as stroke or heart failure. By recognizing triggers, monitoring episodes, and acting quickly when warning signs appear, you can keep the condition in check and protect your long‑term health. Remember, you’re not alone—talk to your doctor, lean on support groups, and use the tools above to stay one step ahead. Got questions or a story to share? Drop a comment below; we’d love to hear from you!








