



Not medical advice — written by Ngoc Vietsmall, who is not a healthcare professional.
This article summarises publicly available medical information for general readers. It cannot account for your history, medication or symptoms, and it is not a diagnosis or a treatment plan. Any dose mentioned comes from published labelling or guidelines — only your own prescriber can decide what is right for you.
Always speak to a doctor or pharmacist before starting, stopping or changing any treatment. If symptoms are severe or getting worse, seek urgent care. Full disclaimer · How this is written
Imagine feeling a sudden, crushing pain in your chest that just won’t go away. It can happen in the blink of an eye, and the underlying problem might be a tiny hole in your esophagus—a condition doctors call esophageal perforation. It’s scary, but knowing what it is, why it happens, and how it’s treated can turn fear into confidence. Let’s walk through everything you need to know, step by step, as if we’re chatting over a cup of coffee.
What Is Perforation?
Definition in Simple Terms
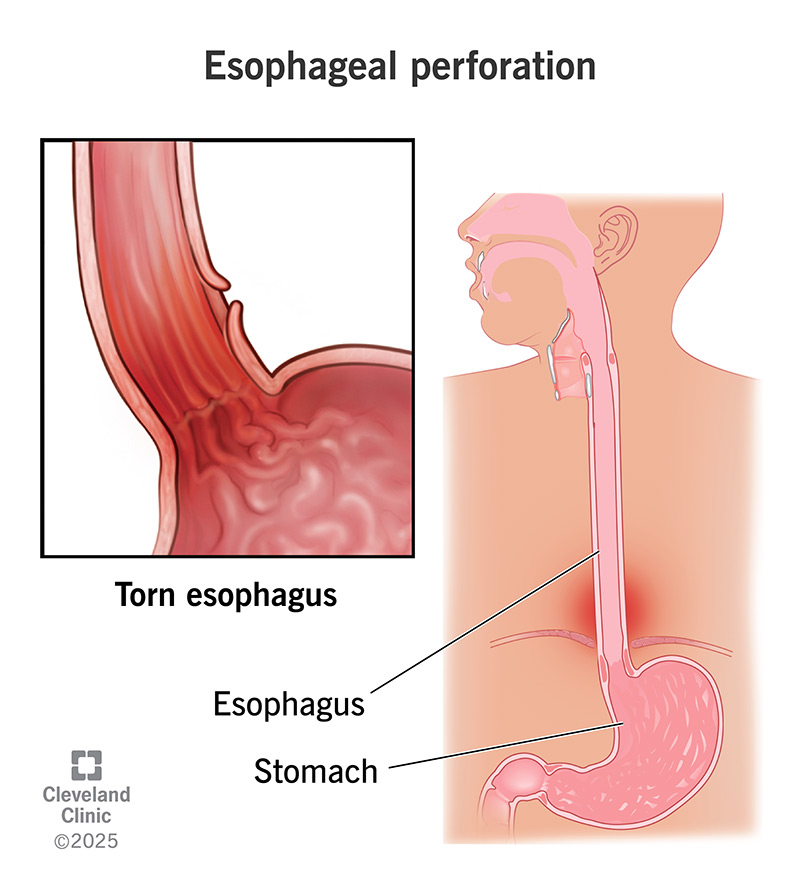
An esophageal perforation is literally a rupture or tear in the tube that carries food from your mouth to your stomach. Think of it like a small hole in a garden hose—water (or in this case, food and fluids) can leak out into the surrounding area, causing irritation, infection, and sometimes serious complications.
Quick Fact Box
| Fact | Detail |
|---|---|
| Incidence | About 3–5 cases per million adults each year. |
| Mortality Range | 5% – 90% depending on speed of treatment (source: Cleveland Clinic). |
| Typical Age | Mid‑30s to 60s, but can happen at any age. |
Why Does It Happen?
Common Iatrogenic Causes
More than half of perforations are iatrogenic—that means they occur during a medical procedure. Upper endoscopy, intubation, and even certain surgeries can unintentionally create a tiny tear. If you’ve recently had an endoscopic exam, this is the most likely culprit.
Spontaneous Rupture (Boerhaave Syndrome)
Ever heard of Boerhaave syndrome? It’s the dramatic name for a spontaneous tear that typically follows violent vomiting or retching. The pressure inside the esophagus spikes, and the wall gives way—usually in the lower third.
Trauma and Foreign Bodies
Penetrating injuries (like a stab wound) or swallowing sharp objects—think fish bones or a piece of glass—can also puncture the esophagus. These cases are less common but equally urgent.
Comparison Table: Causes Overview
| Cause | Typical % of Cases | Usual Scenario |
|---|---|---|
| Iatrogenic (endoscopy, intubation) | ≈56% | Diagnostic or therapeutic procedure |
| Spontaneous (Boerhaave) | ≈15% | Severe vomiting after heavy eating or alcohol |
| Trauma | ≈10% | Penetrating chest/neck injury |
| Foreign body ingestion | ≈8% | Sharp food item lodged in esophagus |
| Other | ≈11% | Rare congenital anomalies |
Spotting the Symptoms
Red‑Flag Warning Signs
If you feel any of the following, treat them as emergency signals:
- Severe, sudden chest or upper‑back pain.
- Neck or chest swelling that feels “crackly” (sub‑cutaneous emphysema).
- Vomiting that doesn’t relieve the pain.
- Fever, rapid heartbeat, or low blood pressure.
These esophageal perforation symptoms often mimic heart attacks or pneumonia, which is why they can be missed initially.
Story From the ER
John, a 48‑year‑old avid baker, went to the ER after a night of heavy drinking and forceful vomiting. He thought the pain was just a sore stomach, but when his neck started to feel "hollow" and his voice sounded muffled, the doctors ordered imaging. It turned out he had a ruptured esophagus—Boerhaave syndrome. Early detection saved his life.
How Doctors Diagnose
First‑Line Tests
Doctors start with a quick blood panel (CBC, lactate) to look for infection and organ stress. Then they move on to imaging.
Imaging Hierarchy
- Chest X‑ray: Can show air in the mediastinum—an early clue.
- Contrast Esophagography: A water‑soluble contrast drink is swallowed; leaking contrast on X‑ray confirms the perforation. If the first study is negative but suspicion remains, a barium swallow may follow.
- CT Scan (with oral contrast): The gold standard. It maps the exact location, size of the leak, and any related infection such as mediastinitis.
Radiology plays a starring role—literally esophageal perforation radiology is the phrase you’ll see in specialist literature.
Endoscopic Confirmation
In some cases, doctors may perform a gentle endoscopy to visualize the tear directly. While it provides a clear picture, it’s used carefully because the scope itself could worsen the injury.
Treatment Options Explained
Immediate Stabilization
First, patients go NPO (nothing by mouth), receive broad‑spectrum antibiotics, and are monitored in an ICU. Think of it as “damage control” before definitive repair.
Conservative Management
If the tear is small (< 2 cm), located in the neck, and diagnosed early (within 24 hours), doctors may opt for non‑operative care—close observation, IV antibiotics, and possibly an esophageal stent to seal the leak.
Surgical Repair Techniques
When the perforation is large, delayed, or causing severe infection, surgery becomes necessary. Common procedures include:
- Primary Repair: Directly suturing the tear, often reinforced with tissue flaps.
- Cervical Exclusion: Diverting food away from the neck wound while it heals.
- Esophagectomy: Removing a damaged segment—reserved for the worst cases.
The choice depends on location (cervical vs. thoracic), size, and how long the leak has been present.
Decision‑Making Algorithm (Quick Guide)
| Factor | Recommended Approach |
|---|---|
| Leak size < 2 cm & early (<24 h) | Conservative + possible stent |
| Leak size ≥ 2 cm or delayed (>24 h) | Surgical repair |
| Location in cervical esophagus | Primary repair or drainage |
| Severe mediastinitis | Urgent thoracic surgery |
What to Expect After Treatment
Hospital stays range from a week (conservative) to several weeks (post‑surgery). Patients usually start on a liquid diet, gradually moving to soft foods as the esophagus heals. Follow‑up swallowing studies are standard to ensure no stricture has formed.
Risks & Prognosis
Mortality and Factors
Can you die from a ruptured esophagus? Unfortunately, yes—mortality can climb to 90% if treatment is delayed beyond 24 hours. However, early diagnosis slashes that risk dramatically, often below 10%.
Common Complications
- mediastinitis (infection of the chest cavity)
- pleural effusion or empyema
- esophageal stricture (narrowing)
- fistula formation to the airway
Long‑Term Outlook
Most survivors return to normal eating within a few months, especially if the leak was small and treated promptly. Ongoing care includes repeat endoscopy or barium swallow to catch any narrowing early.
When to Call Help
Emergency Checklist
If you notice any combination of the following, dial emergency services immediately:
- Sudden, severe chest or upper‑back pain.
- Vomiting that doesn’t relieve discomfort.
- Neck or chest swelling that feels “crackly”.
- Fever, rapid heartbeat, or feeling faint.
Time is the most critical factor—treat it like a heart attack: faster care means better chances of a full recovery.
Coding for Clinicians
ICD‑10‑CM Codes
For accurate medical records and billing, use the following ICD‑10 codes:
| Code | Description |
|---|---|
| K22.3 | Esophageal perforation |
| T81.89 | Other complications of procedures, not elsewhere classified |
| S37.0x | Injury to esophagus (traumatic) |
Documentation Tips
When writing the patient’s chart, be explicit: “Iatrogenic esophageal perforation following upper endoscopy, diagnosed via contrast CT, managed with primary repair”. Clear language helps both clinicians and insurers understand the severity and the care provided.
Conclusion
Living with the possibility of an esophageal perforation can feel overwhelming, but knowledge is a powerful antidote. You now know what the condition looks like, why it happens, how it’s spotted, and the full range of treatments—from careful observation to life‑saving surgery. Most importantly, remember that early detection dramatically improves outcomes; if you ever suspect a leak, don’t wait—call emergency services right away. If you’re a healthcare professional, accurate coding and thorough documentation keep the care chain strong.
Have you or someone you know experienced any of these symptoms? Share your story in the comments or ask any lingering questions—you’re not alone, and together we can turn anxiety into action.








