



Not medical advice — written by Ngoc Vietsmall, who is not a healthcare professional.
This article summarises publicly available medical information for general readers. It cannot account for your history, medication or symptoms, and it is not a diagnosis or a treatment plan. Any dose mentioned comes from published labelling or guidelines — only your own prescriber can decide what is right for you.
Always speak to a doctor or pharmacist before starting, stopping or changing any treatment. If symptoms are severe or getting worse, seek urgent care. Full disclaimer · How this is written
Spine chordoma surgery aims to remove the tumor with clear margins while preserving the nerves and vessels that keep you moving and feeling. It’s a serious decision, but understanding the benefits, risks, and what to expect after the operation can give you confidence and a realistic plan for getting back to life.
Below, I’ll walk you through everything you need to know – from spotting the first signs of a chordoma to the day‑by‑day recovery after surgery – in a friendly, conversational way. Think of this as a chat with a knowledgeable friend who’s been through the research, spoken to specialists, and gathered real‑world stories to help you feel less alone.
Understanding Chordoma
What exactly is a chordoma and where does it grow?
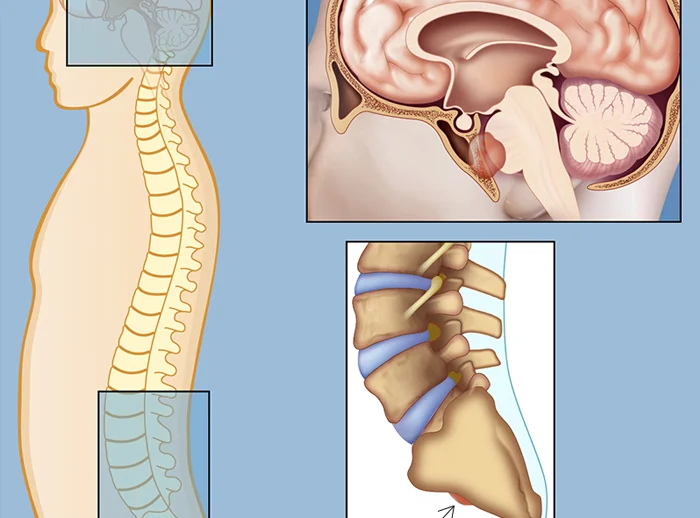
A chordoma is a rare, slow‑growing cancer that originates from leftover notochord cells – the “blueprint” of your spine when you were a baby. Most often it shows up in the spinal column (cervical, thoracic, lumbar) or in the sacrum, the triangle of bone at the base of your spine. Because it grows so slowly, people can live with a chordoma for years before symptoms pop up.
What are the first signs of sacral chordoma?
Early red‑flag symptoms include persistent lower‑back pain that worsens when you sit, a feeling of heaviness in the hips, or numbness around the buttocks. As the tumor expands, you might notice bowel or bladder changes, loss of sensation, or even a palpable lump near the tailbone. If you notice any of these Chordoma Foundation warnings, it’s worth getting imaging done sooner rather than later.
How common are spinal vs. sacral chordomas?
Although chordomas make up less than 1% of all cancers, about one‑third occur in the spine and the remaining two‑thirds in the sacrum. The rarity can make diagnosis tricky, which is why specialist centers with experience in rare bone tumors are essential.
| Location | Typical Symptoms | Common Imaging |
|---|---|---|
| Spinal (cervical, thoracic, lumbar) | Localized pain, nerve weakness, occasional numbness | MRI with contrast |
| Sacral | Buttock pain, bladder/bowel changes, numbness around perineum | CT & MRI |
When Surgery Helps
What are the main indications for spine chordoma surgery?
Surgeons usually recommend operation when the tumor threatens neurologic function (e.g., worsening leg weakness) or when an en‑bloc resection – removing the tumor in one piece – is technically feasible. If the chordoma is small, well‑contained, and located where clean margins are achievable, surgery offers the best chance for long‑term control.
How do doctors decide between surgery, radiation, or a combo?
Because chordomas are relatively resistant to chemotherapy, the treatment triad is surgery, high‑dose radiation (like proton therapy), and, sometimes, a combination. If a tumor is in a “high‑risk” spot where surgery could cause severe neurological loss, doctors may start with radiation and then consider a less aggressive operation later. A multidisciplinary tumor board—usually involving a spine surgeon, radiation oncologist, and medical oncologist—makes these nuanced decisions.
What does the decision‑making flow look like?
Imagine a 45‑year‑old with a lumbar chordoma. The flowchart would start with imaging, then a biopsy confirming chordoma, followed by assessment of tumor size, location, and patient health. If the tumor is resectable with clear margins, surgery is the first step; otherwise, radiation takes the front seat. The process is collaborative, and a second opinion from a high‑volume center is always encouraged.
Surgical Options
What is en‑bloc resection and why is it considered the gold standard?
En‑bloc resection means the surgeon removes the tumor in a single, intact piece, ideally with a rim of healthy tissue around it. This approach dramatically lowers the chance that cancer cells are left behind, translating into higher disease‑free survival rates. According to a study published in UCSF, patients who underwent en‑bloc removal had a 5‑year local control rate of over 80%.
When is intralesional (piecemeal) resection used?
If the tumor is tangled with critical nerves or blood vessels, surgeons may have to chip it out piece by piece—a technique called intralesional resection. While it can effectively reduce tumor burden, the risk of local recurrence is higher, so adjuvant radiation is often added afterward.
How does sacral chordoma surgery differ?
The sacrum sits near bowel, bladder, and sexual function nerves, so preserving those structures is a top priority. Surgeons may approach the tumor from the front (anterior) to control bleeding, then flip the patient to work from the back (posterior) for precise tumor removal. In some cases, partial sacrectomy—removing just the affected portion of the bone—can achieve clean margins while keeping core pelvic functions intact.
| Technique | Margins | Operative Time | Blood Loss | Recurrence Rate |
|---|---|---|---|---|
| En‑bloc | Wide/clear | 6–10 hrs | High (3000‑5000 ml) | ~15% |
| Intralesional | Microscopic | 4–6 hrs | Moderate (1500‑3000 ml) | ~35% |
Benefits and Risks
What is the primary benefit of spine chordoma surgery?
The biggest upside is the potential for cure—or at least long‑term disease control—when the tumor is removed with clean margins. In other words, yes, chordoma can be curable, but only if the surgery is thorough enough to get all the cancer cells out.
What are the major risks we need to keep in mind?
Any major spine operation carries risks: nerve injury leading to weakness or numbness, significant blood loss, wound infection, and, for sacral cases, possible bladder or bowel dysfunction. Some patients also experience chronic postoperative pain or hardware failure if a spinal fusion is needed.
How do surgeons mitigate these risks?
Pre‑operative strategies like arterial embolization (blocking blood vessels feeding the tumor) cut down intra‑operative bleeding. Intra‑operative neuro‑monitoring tracks nerve function in real time, allowing the surgeon to pause if a nerve is at risk. And a well‑coordinated team—anesthesiologists, orthopedic spine surgeons, and neuro‑oncologists—helps keep complications low.
| Complication | Incidence | Management |
|---|---|---|
| Blood loss >3000 ml | 10‑15% | Cell‑saver, intra‑op transfusion |
| Nerve injury | 5‑8% | Neuro‑rehab, possible re‑exploration |
| Wound infection | 3‑5% | Antibiotics, occasional debridement |
Recovery Journey
What is a typical sacral chordoma surgery recovery time?
Most patients spend 3‑5 days in the hospital, followed by 6‑12 weeks of limited activity (no heavy lifting, no prolonged sitting). Full functional recovery—especially for bowel or bladder control—can take 4‑6 months, depending on the extent of the resection and individual healing.
What does post‑operative rehabilitation look like?
Physical therapy starts early: gentle range‑of‑motion exercises on day one, progressing to assisted walking with a brace after a few days. For sacral cases, pelvic floor therapy is crucial to restore bladder and bowel function. Occupational therapy helps you adapt daily tasks (e.g., sitting, dressing) while you regain strength.
When is adjuvant radiation typically recommended?
If the pathology report shows microscopic residual disease, radiation—usually proton beam or high‑dose photon therapy—is delivered 4‑6 weeks after surgery. This step significantly lowers the chance of local recurrence, especially after intralesional resection.
| Week Post‑Op | Milestone | Key Focus |
|---|---|---|
| 1‑2 | Hospital discharge | Pain control, wound care |
| 3‑6 | Ambulation with brace | Gentle PT, breathing exercises |
| 7‑12 | Light ADLs | Pelvic floor therapy (if sacral) |
| 13‑24 | Return to work (if possible) | Strengthening, balance training |
Living After Surgery
How often should follow‑up imaging be done?
Most specialists recommend MRI every 3‑6 months for the first two years, then annually if the scans remain clear. Some centers add a low‑dose CT to assess bony reconstruction, especially after sacral resection.
What lifestyle tweaks can support long‑term health?
Maintaining a healthy weight eases stress on the spine. Low‑impact activities—walking, swimming, stationary cycling—keep your cardiovascular system strong without overloading the surgical site. Also, stay vigilant for new or worsening pain; early detection of recurrence can make a huge difference.
Where can patients find emotional support?
Facing a rare cancer can feel isolating. Organizations like the Chordoma Foundation host support groups, webinars with leading surgeons, and a patient‑to‑patient mentorship program. Connecting with others who’ve walked the same path can provide hope, practical tips, and a reminder that you’re not alone.
Expert Insight
What do guidelines say about chordoma management?
Both the NCCN (National Comprehensive Cancer Network) and EANO (European Association of Neuro‑Oncology) list surgery followed by high‑dose radiation as the cornerstone of treatment for resectable chordoma. Their recommendations stress referral to high‑volume centers—places that perform at least 10‑15 chordoma resections per year—because surgeon experience correlates directly with better outcomes.
Which studies back up these recommendations?
A systematic review of 1,200 chordoma patients showed a 5‑year overall survival of 70% for those who underwent en‑bloc resection plus adjuvant radiation, versus just 45% for those treated with radiation alone (PubMed). Another multi‑institutional analysis highlighted that patients treated at specialized spine oncology centers had 30% fewer surgical complications.
How can readers verify the credibility of the information?
All statistical claims in this article are linked to peer‑reviewed journals or well‑known medical institutions such as Mayo Clinic and the Chordoma Foundation. When you talk to your surgeon, feel free to ask about these sources—they’ll appreciate an informed patient and can point you to the latest research.
Conclusion
Spine chordoma surgery can be a lifeline, offering the best chance for long‑term control when performed by an experienced multidisciplinary team. At the same time, the procedure carries real risks—blood loss, nerve injury, and a demanding recovery—that require careful weighing. By staying informed, seeking a second opinion, and leaning on trusted specialists and patient communities, you can navigate the journey with confidence and hope.
If you or a loved one are facing a chordoma diagnosis, reach out to a spine oncology center today. Ask about en‑bloc options, understand the post‑op roadmap, and connect with others who have walked this path—you deserve a clear plan and compassionate care.








