



Not medical advice — written by Ngoc Vietsmall, who is not a healthcare professional.
This article summarises publicly available medical information for general readers. It cannot account for your history, medication or symptoms, and it is not a diagnosis or a treatment plan. Any dose mentioned comes from published labelling or guidelines — only your own prescriber can decide what is right for you.
Always speak to a doctor or pharmacist before starting, stopping or changing any treatment. If symptoms are severe or getting worse, seek urgent care. Full disclaimer · How this is written
Leukemia cells can sometimes sneak into the brain, spinal cord, or the fluid that cushions themwhat doctors call the central nervous system (CNS). When this happens, its called leukemia CNS involvement. Even though its relatively rare, catching it early can make a huge difference in how you feel and how long you have to enjoy life. Below, Ill walk you through what to look out for, how doctors figure it out, what the numbers say about survival, and the treatment options that are out there.
How Common Is It
Most people think of leukemia as a bloodonly disease, but the CNS can become a hidden sanctuary for cancer cells. Studies show that less than 10% of adult patients have CNS involvement at the time of diagnosis, and the rate can rise to about 20% when doctors routinely test the cerebrospinal fluid (CSF). The odds arent the same for every type of leukemia:
- Acute lymphoblastic leukemia (ALL): roughly 5% at presentation.
- Acute myeloid leukemia (AML): about 23% initially, but higher in certain highrisk subtypes.
Risk climbs if you have a very high whitecell count, specific genetic changes (like the Philadelphia chromosome), or if the disease has already spread outside the bone marrow. Knowing these red flags helps both patients and doctors stay one step ahead.
Recognizing CNS Symptoms
These symptoms can feel like anything from a simple migraine to a fullblown neurological emergency. Heres a quick checklist of all CNS involvement symptoms you might notice:
- Persistent, worsening headachesespecially in the morning.
- Nausea or vomiting that isnt related to treatment.
- Blurred vision, double vision, or sudden loss of visual fields.
- Facial weakness, drooping, or other cranialnerve palsies.
- Newonset seizures or brain fog.
- Unsteady gait, clumsiness, or trouble with coordination.
- Confusion, memory lapses, or personality changes.
These signs can easily be brushed off as side effects of chemotherapy, stress, or even a flu. Thats why it matters to bring any new neurological symptom to your oncologist right away.
When Symptoms Mimic Other Conditions
Because headaches and fatigue are common in anyone dealing with cancer, distinguishing cns leukemia symptoms from medication sideeffects, infections, or a stroke is tricky. Doctors rely on a combination of timing (sudden vs. gradual), severity, andmost importantlyobjective testing to tell the difference.
Diagnosing CNS Involvement
Getting a solid diagnosis usually means two things: a look inside the fluid that bathes the brain (the CSF) and a peek at the brain itself with imaging.
Lumbar Puncture & CSF Analysis
The goldstandard test is a lumbar puncture, where a thin needle draws a small amount of CSF from the lower back. The fluid is examined under a microscope (cytology) and often run through flow cytometry (MFC) to detect even a few cancer cells. In most guidelines, finding 5% or more blasts in the CSF is considered positive for CNS disease.
NeuroImaging (Radiology)
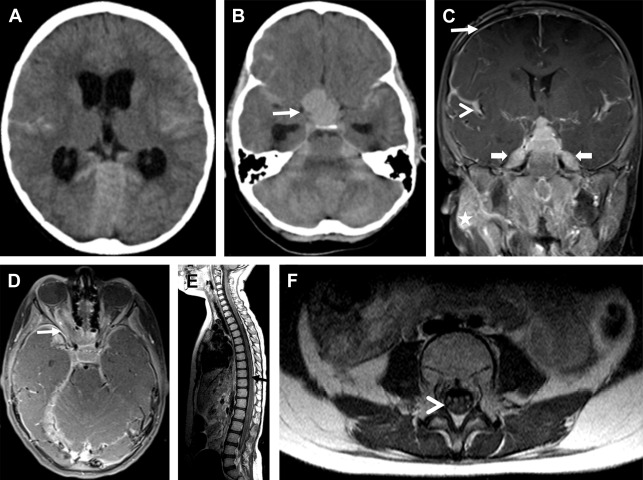
Magnetic Resonance Imaging (MRI) with contrast is the goto scan. It can reveal leptomeningeal enhancement (the thin membranes covering the brain) or small chloromas that sometimes form in the spine. If a patient cant have an MRIsay, because of a pacemakerCT with contrast is the backup, though its less sensitive.
Radiology Example
Radiopaedias article on leukemia CNS manifestations includes illustrative MRI slices that show the typical patterns doctors look for.
Other Helpful Clues
Blood tests that show a rising lactate dehydrogenase (LDH) level, plus cytogenetic or molecular studies (like BCRABL testing), can help paint a fuller picture of how aggressive the disease might be.
Survival Outlook Overview
Survival numbers can feel cold, but theyre essential for planning and hopesetting. In adult patients with CNSpositive ALL, the median overall survival is around 12 months, compared with more than 24 months when the CNS is untouched. For AML with CNS involvement, the twoyear overall survival hovers between 30% and 40%. These figures come from recent multicenter studies (e.g., Haematologica 2022, Blood 2024).
Key Prognostic Factors
Several variables sway the odds:
- Age (younger patients tend to do better).
- Performance statushow well youre able to carry out daily activities.
- Number of blasts in the CSF after induction therapy.
- Underlying genetics (highrisk cytogenetics like t(9;22) worsen prognosis).
- Whether you achieve a complete remission in the CNS (CNS CR).
| Factor | Favorable | Unfavorable |
|---|---|---|
| Age | <60y | 60y |
| CSF blast % after induction | <5% | 5% |
| Highrisk cytogenetics | Absent | Present |
| CNS Complete Remission | Achieved | Not achieved |
Seeing a favorable column ticked off gives us a reason to be optimistic, but remember that each persons journey is unique.
Treatment Options Explained
When leukemia takes a detour into the CNS, the therapeutic game plan becomes a mix of local and systemic weapons. The goal is to wipe out the cancer cells hiding in the brain while protecting the delicate nervous tissue.
Intrathecal Chemotherapy (IT)
Think of IT as delivering a oneonone punch directly into the CSF. The usual cocktailmethotrexate, cytarabine, and hydrocortisonegets poured into the spinal canal several times during each chemotherapy cycle (often on days1,8,15). Because the bloodbrain barrier blocks many drugs, this method is essential for reaching the sanctuary sites.
HighDose Systemic Chemotherapy
Some drugs, like highdose methotrexate or cytarabine, can cross the bloodbrain barrier in larger amounts. These are usually given in specialized highdose protocols that require extra monitoring for kidney function and neurotoxicity.
Targeted & Immunotherapy
Newer agents have added a bright splash of hope:
- Blinatumomab (a CD19directed bispecific Tcell engager) has shown activity against CNS disease in ALL.
- CART cell therapystill early in adult trialsbut the 2024 pilot data suggest it can reach the CNS and achieve deep remissions.
Radiation Therapy (CNSDirected)
Wholebrain or craniospinal irradiation is reserved for cases that dont respond to chemotherapy or when theres a bulky lesion. While radiation can be lifesaving, it also carries risks of longterm cognitive changes, so doctors weigh the benefits carefully.
Case Story: AML with CNS Involvement
One 52yearold patient with AML and a positive CSF blast count underwent MFCguided intrathecal therapy combined with highdose cytarabine. Within six weeks, the CSF was clear, and the patients neurologic symptoms faded. An expert hematologist highlighted the importance of close toxicity monitoringespecially for hearing loss and peripheral neuropathy.
Supportive Care & Toxicity Monitoring
Even the best regimen can cause side effects. Common issues include:
- Neurocognitive testing to catch early signs of chemo brain.
- Bloodsugar spikes from steroids.
- Infection riskCSF taps can introduce bacteria, so sterile technique is a must.
Regular followup with both your oncologist and a neurologist ensures that any problem gets addressed before it snowballs.
Frequently Asked Questions
What are the first signs of CNS leukemia?
New, persistent headaches, seizures, visual changes, or facial weakness are often the earliest clues.
How is CNS leukemia confirmed?
A lumbar puncture with CSF cytology/flow cytometry, paired with an MRI of the brain or spine, gives the definitive answer.
Can CNS leukemia be cured?
Up to 80% of patients achieve complete remission with combined intrathecal and systemic therapy, but longterm cure depends on leukemia type and risk factors.
Is radiation always needed?
Nomost patients respond to chemotherapy alone. Radiation is usually saved for relapsed or refractory disease.
What is the survival outlook for adults?
Median overall survival ranges from 12 to 24months; catching the disease early and treating aggressively can improve those numbers.
Balancing Risks & Benefits
Every treatment comes with a tradeoff. Intrathecal chemotherapy can prevent permanent neurologic damage but may cause chemical meningitis or nerve irritation. Wholebrain radiation can halt disease progression but might affect memory and concentration later on. The best approach is a shared decisionmaking conversation with your care teamask about the chances of remission, the potential side effects, and how the treatment fits into your life goals.
One patient I spoke with described the experience as like walking a tightrope: every step needs careful balance, but the view from the other sidebeing cancerfreeis worth the effort. That metaphor captures the emotional stakes: youre weighing immediate risks against longterm hope.
Helpful Resources & Next Steps
If you or a loved one is dealing with leukemia CNS involvement, here are some practical actions:
- When to seek help: Any new neurologic symptomheadache, vision change, seizurewarrants immediate evaluation.
- Ask your doctor: What is my CNS disease status? What tests will you use? What are the goals of treatment?
- Explore reputable sources: The NCCN Guidelines (2024) and the Leukemia & Lymphoma Societys fact sheets give clear, uptodate information.
- Consider a second opinion: A neurooncology specialist can provide perspective on complex cases, especially when radiation or CART therapy is on the table.
Remember, staying informed and connected with a supportive care team empowers you to make the best choices for your health. If you have questions, reach out to your oncologist or a trusted patientadvocacy groupyoure not alone in this journey.
Weve covered the basics of leukemia CNS involvement, from how often it shows up to the signs that should set off alarms, the diagnostic steps, survival statistics, and the treatment toolbox. Keep these takeaways in mind, talk openly with your doctors, and stay hopefulmedical science is continually advancing, and many people are now living longer, fuller lives even after a CNS diagnosis.








