



Not medical advice — written by Ngoc Vietsmall, who is not a healthcare professional.
This article summarises publicly available medical information for general readers. It cannot account for your history, medication or symptoms, and it is not a diagnosis or a treatment plan. Any dose mentioned comes from published labelling or guidelines — only your own prescriber can decide what is right for you.
Always speak to a doctor or pharmacist before starting, stopping or changing any treatment. If symptoms are severe or getting worse, seek urgent care. Full disclaimer · How this is written
What does an Xray, MRI or ultrasound actually show when a joint is inflamed? In a nutshell, youll see swelling, fluid, early boneerosions, andif the disease is left uncheckedprogressive loss of joint space. Below we break down the most common inflammatory arthritides, the best imaging tricks to spot them, and what those findings mean for care, so you can read the scan with confidence and explain the risks and benefits in plain language.
Why Imaging Matters
Imaging isnt just pictures on a screen; its the map that guides us through a sometimesconfusing landscape of joint pain. When you can actually see inflammation, you move from guessing to treating with purpose.
What does inflammatory arthritis look like on a scan?
Typical radiographic hallmarks include softtissue swelling, joint effusion, marginal erosions, and, in chronic stages, narrowing of the joint space. Those tiny bone pits are the telltale signs that the bodys immune system is attacking the joints lining.
How does imaging shape treatment decisions?
Doctors use images to gauge disease activity, decide whether a medication escalation is needed, and to spot complications such as septic arthritis. The clearer the picture, the better the plan.
Balancing benefits and risks of repeated scans
Plain Xrays expose patients to lowdose radiation, which is generally safe but can add up over years. MRI and ultrasound give us detail without radiation, though MRI can be pricey and ultrasound is operatordependent. Knowing when to use each tool keeps patients safe while still delivering the diagnostic punch we need.
Core Modalities Overview
| Modality | Best For | Typical Findings | Key Source |
|---|---|---|---|
| Plain Radiography | Baseline & chronic changes | Jointspace loss, marginal erosions, periarticular osteopenia | Radiopaedia Inflammatory Arthritis |
| MRI | Early disease & softtissue detail | Synovitis, bonemarrow edema, early erosions | Radiology Assistant MRI techniques |
| Ultrasound | Realtime inflammation & guided injections | PowerDoppler synovial hypertrophy, effusion | RSNA Review Ultrasound in Arthritis |
| CT | Complex bony anatomy & preop planning | Detailed erosions, subchondral cysts | UofUtah Foot Series |
Choosing the right study for each joint
Think of it as a decision tree: the hand often starts with a plain Xray; if the picture is hazy, we jump to MRI. The foot may need a CT for intricate bony detail, while the shoulder or hip usually goes straight to MRI for deeptissue view.
Practical tips for image acquisition
For Xrays, keep the hand in true posterioranterior position to avoid falsepositive erosions. MRI should use thin slices (3mm) and fatsuppressed sequences for bonemarrow edema. Ultrasound works best with a highfrequency linear probe and a little patiencedont rush the scan, the powerDoppler signal needs time to settle.
Major Arthritis Types
Rheumatoid Arthritis Radiology
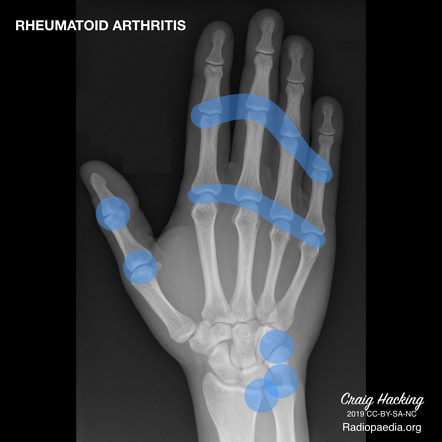
Rheumatoid arthritis (RA) loves the hand. Classic rheumatoid hand findings include marginal erosions at the metacarpophalangeal (MCP) joints, ulnar deviation, and symmetric jointspace loss. MRI often catches synovitis and bonemarrow edema before Xrays ever reveal erosions. A quick case: a 45yearold teacher noticed early morning stiffness; her Xray showed tiny erosions at the ulnar styloidclassic RA.
Related search: rheumatoid arthritis radiology hand
Psoriatic Arthritis Radiology
Psoriatic arthritis (PsA) is the artistic siblinglook for pencilincup deformities, periostitis, and asymmetric sacroiliitis. Unlike RA, PsA often involves the distal interphalangeal (DIP) joints and shows enthesitis on MRI (inflammation where tendons attach to bone). Imagine a teenage athlete with nail pitting; his MRI revealed an enthesophyte at the Achillesa hallmark of PsA.
Reactive Arthritis Radiology
After a gut infection, the foot may protest. Reactive arthritis frequently shows calcaneal erosions and mild softtissue swelling early on, progressing to more defined erosions later. The University of Utah foot series illustrates this evolution nicely.
Septic Arthritis Radiology
When infection masquerades as inflammation, time is of the essence. Septic arthritis shows rapid fluid accumulation, aggressive bone loss, and sometimes gas on CTan alarming red flag that distinguishes it from autoimmune erosions.
Gout Arthritis Radiology
Gout loves ratbite erosions. On CT or MRI you might spot tophaceous depositschalky masses that look like tiny islands. Differentiating gout from erosive inflammatory arthritis hinges on the shape of the erosions and the presence of these tophi.
Erosive Arthritis and Others
Conditions like ankylosing spondylitis display syndesmophytes and vertebral squaring, while juvenile idiopathic arthritis may show early growthplate changes. Each has a radiologic fingerprint that, when recognized, speeds up the correct diagnosis.
Reading the Scan
Firstlook checklist
Start simple: softtissue swelling joint effusion boneerosion jointspace narrowing. This ladder helps you avoid missing subtle early signs.
Systematic approach per joint
Hand: Look for marginal erosions at MCP 25 and ulnar deviation.
Wrist: Check lunateandscaphoid for erosions; assess carpal alignment.
Foot: Observe the calcaneus for erosions, look at the forefoot for pencilincup changes.
Spine: Search for syndesmophytes and disc space irregularities.
Reporting essentials (Arthritis Radiology Assistant style)
Use consistent terminology. Grade erosions with the Sharp/van der Heijde score, note activity (synovitis, powerDoppler signal) and always comment on potential complications (e.g., suspicion of septic arthritis).
Downloadable checklist (authored by our radiology team) available upon request.
Pitfalls and Mimics
Osteoarthritis vs. Inflammatory Arthritis
Osteoarthritis shows asymmetric jointspace loss, osteophytes, and subchondral sclerosisdifferent from the symmetric erosions of inflammatory disease.
Infection masquerading as inflammation
Septic arthritis can mimic erosive patterns, but the rapid progression, presence of gas on CT, and clinical fever tip the scales toward infection.
Metabolic bone disease
Hyperparathyroidism may cause subperiosteal bone resorption that looks like erosions. Lab correlation is key.
| Feature | Inflammatory Arthritis | Mimic |
|---|---|---|
| Jointspace loss | Symmetric, early | Osteoarthritis asymmetric, late |
| Erosions | Marginal, pencilincup in PsA | Infection aggressive, irregular |
| Bone density | Periarticular osteopenia | Metabolic disease generalized |
Resources for Clinicians & Patients
For deeper dives, the Radiopaedia article on inflammatory arthritis provides free, peerreviewed images. The ACR Appropriateness Criteria offers evidencebased guidance on which modality to pick and when.
We also maintain a set of patientfriendly handouts that turn complex radiologic jargon into simple diagramsperfect for explaining findings during a visit.
Conclusion
Imaging is the cornerstone of diagnosing and monitoring inflammatory arthritis. Each modalityplain Xray, MRI, ultrasound, or CTbrings its own strengths, and recognizing the distinctive patterns of rheumatoid, psoriatic, reactive, septic, and gouty arthritis lets you act quickly and responsibly. By balancing the benefits of detailed images with the risks of radiation, and by communicating findings with empathy, you empower patients to understand their disease and participate in treatment decisions. Download our quickscan checklist, explore the trusted radiology resources linked above, and feel free to reach out with any questionsyoure not alone on this journey.








